Understand the fascia, rule out other causes and return to tolerable walking
Pain beneath the heel, particularly during the first steps after rest, may be consistent with plantar fasciopathy. The term “fasciitis” remains common, but persistent pain is not necessarily explained by inflammation alone. Diagnosis brings together the location, behaviour of symptoms and examination findings. Not all heel pain comes from the fascia. [1] [2]
Management aims to restore weight-bearing capacity that supports the activities the person wants to do. It generally combines load adjustment, exercise and aids selected for the individual. No single shoe, stretch or manual treatment automatically resolves every presentation. Progress is judged in daily life and by how well improvements last. [1] [3]
Anatomy: a supportive tissue exposed to load
The plantar fascia is a fibrous structure beneath the foot. It connects the heel region to the forefoot and contributes to arch support and force transmission during walking. It works with muscles, tendons and joints; it is not an independent cable that simply needs to be loosened. [4]
Tension developing as the toes extend contributes to the mechanism often called the windlass. This helps explain foot function but cannot attribute pain to one particular arch shape. Wearing’s review highlights uncertainties surrounding some traditional biomechanical explanations. A flat or high-arched foot is therefore not a diagnosis in itself. [4]
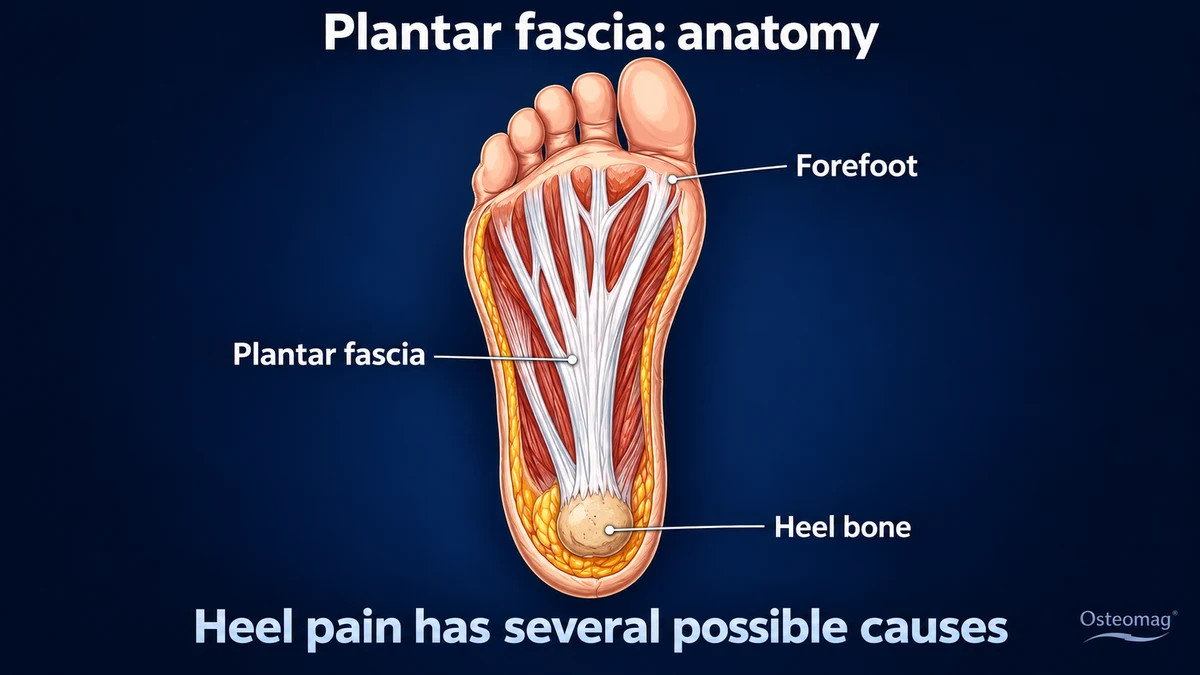


In persistent presentations, tissue changes and sensitivity cannot be reduced to an ongoing tear. Pain is not a microscope: its intensity does not directly measure the state of the fascia. An assessment can identify a compatible clinical pattern and guide care without claiming to describe every cellular change. The language used should support useful understanding rather than a constant fear of damaging the foot. [1] [4]
Why does pain start or persist?
An increase in walking, running, standing or jumping may temporarily exceed the foot’s tolerance. Work demands, recovery and everyday activities matter alongside training. Some mechanical factors, such as reduced ankle dorsiflexion or strength, may be associated with the presentation without explaining every case or proving a single cause. [5]
Body weight may also contribute to loading, but it should not become a blaming explanation or a prerequisite for receiving care. A person needs a workable plan that fits their health, employment and resources. Assessment primarily looks for factors that can usefully be adjusted, rather than compiling a list of presumed postural imperfections. [5]
Persistent pain may alter walking. This does not prove a secondary knee or back injury: the experience of pain and tissue damage are not equivalent. [6]
Typical symptoms and alternative diagnoses
The classic pattern includes plantar pain near the inner heel attachment, often more marked during the first steps after rest. It may ease as movement begins and return with prolonged loading. The clinician examines this behaviour and local tenderness. Diffuse or unusual pain warrants a broader assessment. [2]
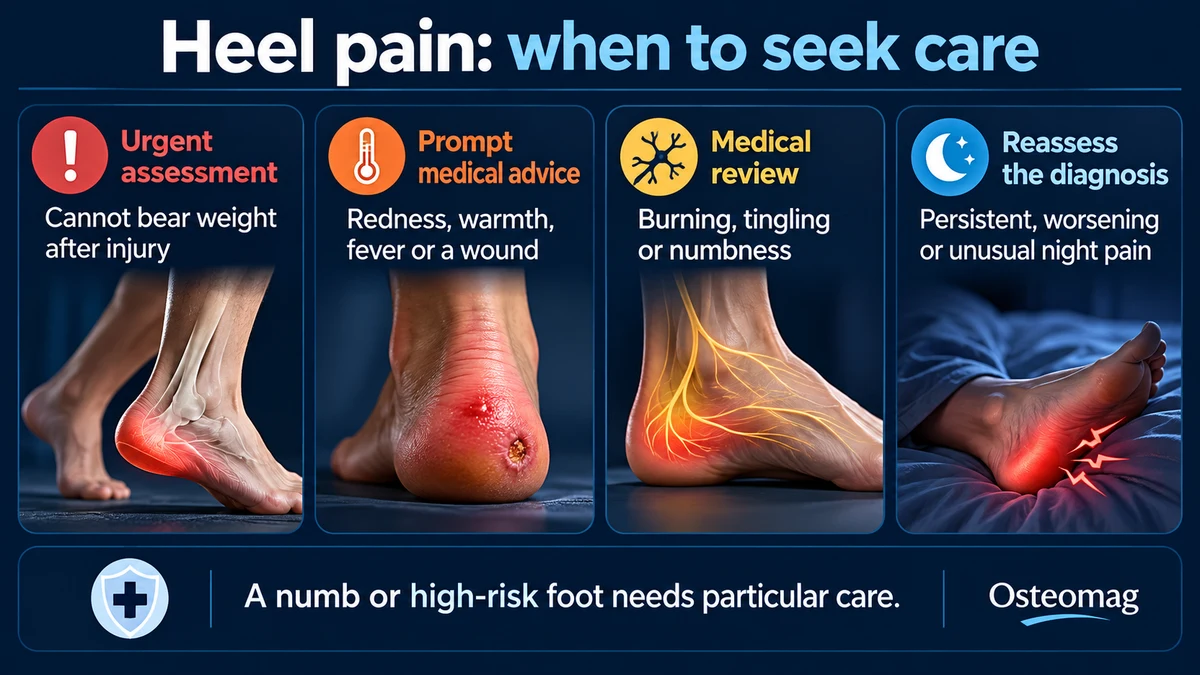
Central, bruise-like pain may suggest the heel fat pad. Progressive bony pain after an increase in loading may prompt investigation for a stress fracture. Burning, tingling or numbness suggests a possible nerve component. Pain behind the heel may involve the Achilles tendon or neighbouring tissues rather than the fascia. [2]
Bilateral pain accompanied by other inflammatory features, unusual stiffness or general symptoms requires an appropriate assessment. A neurological cause, infection or another condition is not excluded by calling the problem “fasciitis”. The diagnosis should be reconsidered when the course and examination do not fit the expected presentation. [1] [2]
Clinical examination and the role of imaging
The history establishes the location, onset, first-step symptoms, activity volume and work demands. Examination may assess walking, tenderness, ankle movement and muscle capacity. Tensioning the fascia may contribute to clinical reasoning, but no self-test replaces differential diagnosis. Findings are interpreted together. [1] [2]
Imaging is not routine. X-ray, ultrasound or MRI may investigate a suspected cause or an unusual course. A spur or thickened fascia is insufficient to explain an individual’s difficulties. [2] [7]
A heel spur is a bony growth that may also be seen in people without pain. The American College of Foot and Ankle Surgeons consensus notes that a spur does not automatically change initial management. Its disappearance should not be presented as necessary for comfortable walking. [7]


Adjust load without an all-or-nothing approach
The first step is to identify a tolerable amount of activity. Breaking walks into shorter sessions, alternating tasks and temporarily reducing the most irritating activities can preserve useful participation. Prolonged complete rest followed by a sudden return is rarely a satisfactory plan. The best practice guide proposes a gradual approach combining education and appropriately chosen interventions. [3]
At work, a short seated break, task rotation or a change in weight-bearing may be more realistic than a vague instruction to rest. At home, trying a comfortable shoe on getting up may help when barefoot walking increases symptoms. A solution is judged by its actual effect; it does not need to claim permanent correction of foot shape.

Exercise: stretching and strengthening to suit the presentation
Plantar fascia-specific stretching has been studied in chronic heel pain. A trial by DiGiovanni and colleagues reported favourable outcomes in a defined setting. This supports discussing it clinically without prescribing the same range or frequency to everyone. Gentle stretching may be tried; sharp pain is not a goal. [8]
One example is to sit, support the foot and gently move the toes until a moderate tension is felt in the arch. Duration and repetitions are individualised. A calf-stretching variation may be chosen when a relevant limitation is found. People should be able to stop without believing that departing from a universal dosage will compromise recovery.
Progressive calf and foot strengthening aims to develop weight-bearing capacity. A small randomised trial investigated high-load training, with faster improvement in some short-term outcomes. It does not show that everyone should start with heavy loading or that this programme guarantees better long-term results. [9]
Progression may begin with supported heel raises on both feet and become more demanding if the response is acceptable. The starting point considers balance, pain and other health conditions. The strengthening review highlights limited evidence; the programme is therefore adapted rather than promising measurable reconstruction of the fascia. [10]


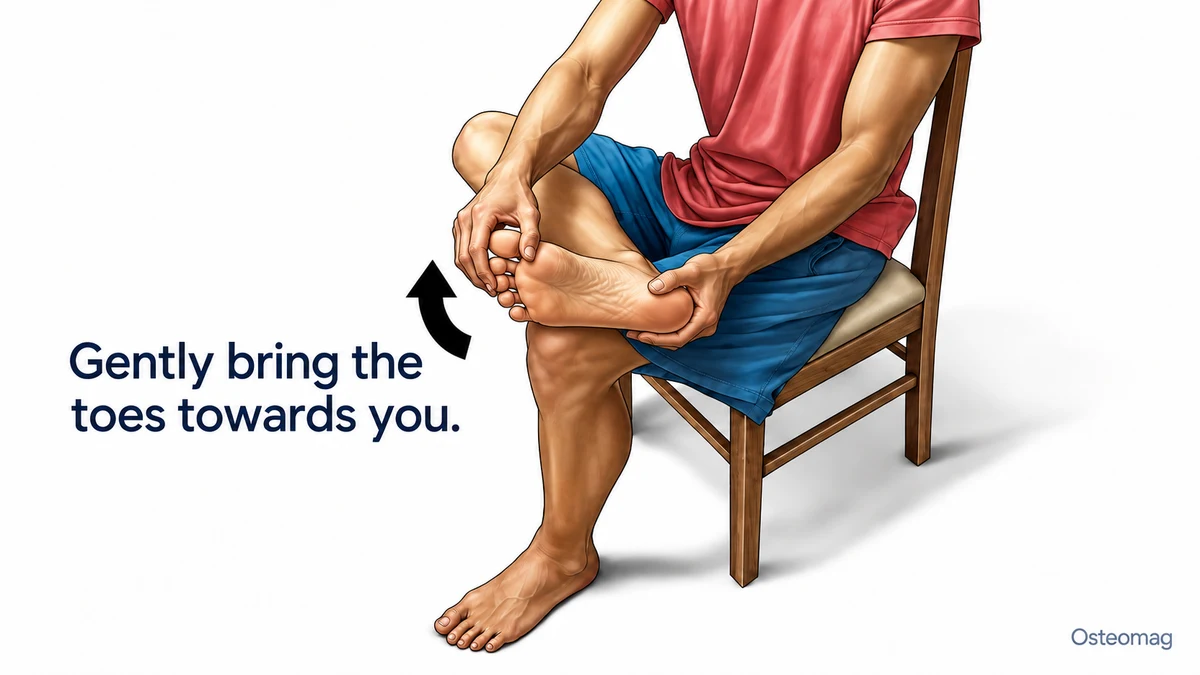


Table: following useful progress
| Goal | Possible starting point | What guides adjustment |
|---|---|---|
| More comfortable first steps | Tolerable footwear and gentle preparatory movement | Morning discomfort and week-to-week change |
| Walk farther | Short, divided walking sessions | Tolerance during walking and the next day |
| Build weight-bearing capacity | Adapted, supported heel raises | Control, fatigue and delayed response |
| Work while standing | Alternate tasks and realistic breaks | Ability to finish the working day |
| Return to running | Gradual programme after assessment | Function, recovery and no lasting aggravation |
Footwear, orthoses and complementary aids
Comfortable footwear suited to the activity may make weight-bearing easier. Orthoses may be tried as an adjunct when they address a concrete goal. The reviews by Whittaker and Rasenberg report results that vary with comparators and follow-up times. They do not support the idea that an expensive or custom-made orthosis is necessarily better for everyone. [11] [12]
Taping may provide temporary help for some people. Night splints suit particular presentations, including pronounced first-step pain. When initial measures are insufficient, specialist discussion of options such as shockwave therapy may be appropriate. Choice depends on assessment and preferences, with realistic expectations. [1] [3]

Osteopathic care and the evidence
The osteopath begins with the symptoms, warning signs and available diagnosis. They observe difficult activities and agree on a goal with the person: more walking, more comfortable first steps or a better-tolerated working day. Atypical pain or suspected stress fracture calls for referral rather than immediate manual care. The osteopath does not provide the medical diagnosis.
Where appropriate, gentle work on the calf or foot muscles may be offered for comfort, without aggressive pressure on an irritable area. Load advice and exercise remain central. Manual care does not claim to remove a spur, tear adhesions, restore inadequate circulation or put the pelvis back into place.
A systematic review of manual therapy for plantar fasciitis suggests possible benefits, with heterogeneous studies and frequent combinations with other interventions. These findings do not validate every proposed osteopathic mechanism or a universal standalone treatment. Function should be reassessed, and an intervention that provides no useful help should be discontinued. [13]

References
- [1] Koc TA Jr et al. Heel Pain—Plantar Fasciitis: Revision 2023. J Orthop Sports Phys Ther, clinical practice guidelines. PubMed
- [2] Tu P. Heel Pain: Diagnosis and Management. American Family Physician, 2018. PubMed
- [3] Morrissey D et al. Management of plantar heel pain: a best practice guide informed by a systematic review, expert clinical reasoning and patient values. Br J Sports Med, 2021. PubMed
- [4] Wearing SC et al. The pathomechanics of plantar fasciitis. Sports Medicine, 2006. PubMed
- [5] Sullivan J, Pappas E, Burns J. Role of mechanical factors in the clinical presentation of plantar heel pain: Implications for management. Foot, 2020. PubMed
- [6] Raja SN et al. The revised International Association for the Study of Pain definition of pain. Pain, 2020. PubMed
- [7] Schneider HP et al. American College of Foot and Ankle Surgeons Clinical Consensus Statement: Diagnosis and Treatment of Adult Acquired Infracalcaneal Heel Pain. J Foot Ankle Surg, 2018. PubMed
- [8] DiGiovanni BF et al. Tissue-specific plantar fascia-stretching exercise enhances outcomes in patients with chronic heel pain. J Bone Joint Surg Am, 2003. PubMed
- [9] Rathleff MS et al. High-load strength training improves outcome in patients with plantar fasciitis: a randomized controlled trial with 12-month follow-up. Scandinavian Journal of Medicine & Science in Sports, 2015. PubMed
- [10] Huffer D et al. Strength training for plantar fasciitis and the intrinsic foot musculature: A systematic review. Physical Therapy in Sport, 2017. PubMed
- [11] Whittaker GA et al. Foot orthoses for plantar heel pain: a systematic review and meta-analysis. Br J Sports Med, 2018. PubMed
- [12] Rasenberg N et al. Efficacy of foot orthoses for the treatment of plantar heel pain: a systematic review and meta-analysis. Br J Sports Med, 2018. PubMed
- [13] Fraser JJ et al. Does manual therapy improve pain and function in patients with plantar fasciitis? A systematic review. Journal of Manual & Manipulative Therapy, 2018. PubMed