Understanding bony growths without confusing an imaging finding with the cause of pain
An osteophyte is a bony formation that develops, particularly at the edge of a joint or vertebral body. It often accompanies osteoarthritic changes, but finding one does not automatically mean that it causes symptoms. Many people live with degenerative changes without substantial pain. The useful question is therefore whether the image matches the history, examination, and difficulties experienced. [1] [2]
The term “bone spur” can suggest a sharp point continually injuring tissues. This picture is often too simple. Depending on its location and context, an osteophyte may remain silent, contribute to restricted movement, or play a role in compression. Care first addresses relevant function and symptoms; it does not necessarily involve making an imaging finding disappear.
Anatomy and osteophyte formation
A joint combines cartilage, subchondral bone, synovial membrane, capsule, ligaments, and muscles. These structures respond together to loading. Osteoarthritis affects the whole joint and is not simply passive cartilage wear. Bone remodeling processes and biological signals contribute to osteophyte formation. [1] [2]
An osteophyte may contain a cartilage component during development and later ossify. Its formation does not require all cartilage to have disappeared or two bones to rub directly against each other. Mechanical factors, joint history, age, and individual susceptibility interact. It would be excessive to attribute every osteophyte to a particular posture or a muscle judged to be too tense.
In the spine, growths may appear at the margins of vertebral bodies or posterior joints. Their proximity to a canal or foramen can be clinically important. However, an anterior growth far from nerve structures does not have the same implications as narrowing that matches a neurological deficit.
Osteophytes, enthesophytes, and syndesmophytes: different findings
Not all peripheral bony formations are osteophytes in the same sense. An enthesophyte develops at a tendon or ligament attachment. Some heel spurs fall into this category. A syndesmophyte represents another form of ossification, discussed particularly in certain inflammatory spinal diseases. These terms describe different contexts and should not be used interchangeably.
A growth alone therefore does not diagnose osteoarthritis or an inflammatory disease. A report may require explanation, especially when several terms are combined. An atypical bony mass, rapid progression, or unusual symptoms calls for a specific analysis rather than automatically applying an osteoarthritis program.
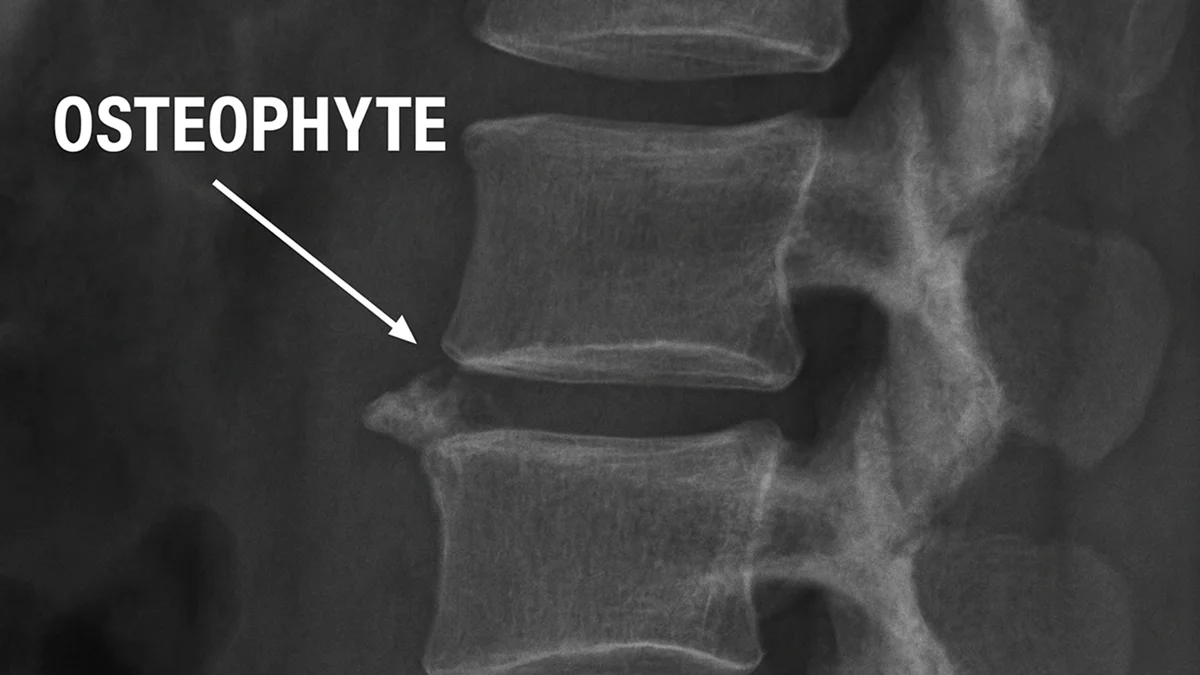
The anatomical illustration retained in this article shows different degrees of growth on vertebrae. It describes morphology; it does not provide a scale of pain, disability, or need for surgery.


Why pain does not always follow the image
Osteoarthritis pain may involve the synovium, subchondral bone, tissues around the joint, and nervous system sensitivity mechanisms. [3] Strength, sleep, activity load, and life circumstances also influence its impact. An osteophyte may contribute to a presentation without being its sole explanation.
Spinal imaging research shows that many degenerative changes are common in people without pain and increase with age. [4] This does not make every abnormality insignificant: it means that interpretation is necessary. An image and a symptom occurring together do not, by themselves, demonstrate a causal relationship.
For the hip, a recent systematic review found variable associations between MRI abnormalities and pain. [5] The evidence is more convincing for some lesions than for others. It is therefore preferable to discuss clinical concordance and uncertainty rather than promise a complete explanation based on osteophyte size.


Manifestations in different regions
At the knee or hip, discomfort may take the form of pain with certain loads, stiffness after rest, or reduced movement range. Difficulties may involve walking, stairs, or dressing. In the fingers, joint enlargement can accompany osteoarthritis, but recent swelling that is hot and very painful requires consideration of other causes.
In the cervical or lumbar spine, some bony formations contribute to narrowing around a nerve root or the spinal cord. Radiating pain, numbness, or weakness must be analyzed according to its distribution and the examination. [6] Not every spinal osteophyte compresses a nerve, and not every limb pain is caused by a spinal imaging finding.
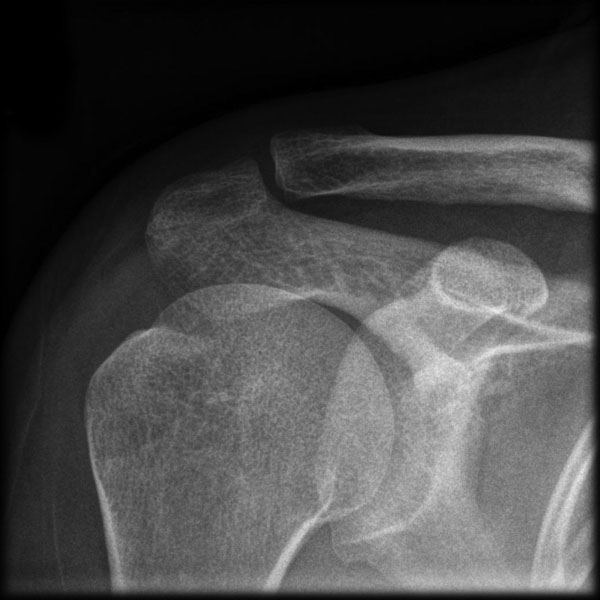
At the shoulder, a subacromial spur alone does not demonstrate that a tendon is mechanically “pinched” during every movement. Rotator cuff-related pain mechanisms are more complex. More rarely, large anterior cervical formations may contribute to swallowing difficulty, but this requires a specific assessment and should not immediately be attributed to the spine.
Clinical examination: looking for concordance
The interview clarifies the location, onset, progression, triggering activities, and associated symptoms. The practitioner asks what has become difficult and what remains possible. Pain that begins suddenly after a fall cannot simply be explained by a previously known, longstanding osteophyte.
The examination observes active and passive movements, strength, and useful tasks. An effusion, warmth, or substantial limitation guides clinical reasoning. If neurological signs are present, an appropriately qualified professional may assess strength, sensation, reflexes, and gait. No single test can establish that a particular osteophyte is the source of all the pain.
Clinical criteria for knee osteoarthritis can often guide diagnosis without multiplying investigations. [10] A cracking or grinding sensation is not, by itself, evidence of ongoing destruction. Monitoring should focus on function and progression rather than the sound a joint produces.
Clinical presentation: several diagnoses remain possible
| Presentation | Possibility to consider | Limits and referral |
|---|---|---|
| Pain with certain loads, stiffness, and progressive limitation | Symptomatic osteoarthritis | The osteophyte supports the context but does not measure pain |
| Localized pain during tendon loading | Tendinopathy or a periarticular problem | Can coexist with osteoarthritis; functional examination is needed |
| A very hot, swollen, suddenly painful joint | Infection or crystal arthritis | Urgent assessment according to context; do not assume a simple osteoarthritis flare |
| Radiating pain with sensory disturbance or weakness | Nerve root or peripheral nerve involvement | Check neurological concordance and obtain imaging when indicated |
| Hand clumsiness and unstable walking | Possible cervical myelopathy | Prompt medical advice; urgent assessment if substantial worsening occurs |
| Pain after trauma or at rest with systemic signs | Fracture, infection, or another condition | Targeted investigation; a degenerative finding should not divert attention |
Red flags and situations requiring referral
Progressive weakness, new difficulty walking, or increasing hand clumsiness may suggest cervical spinal cord involvement and warrants prompt assessment. [7] Loss of perineal sensation or a new bladder control disturbance associated with spinal pain requires urgent assessment. These symptoms should not be monitored solely through comfort-focused treatment sessions.
A red, very painful, swollen joint, particularly with fever or malaise, requires investigation for infection. Absence of fever is not enough to exclude it. Significant trauma, inability to bear weight, or new bone pain in someone at risk of fracture also needs specific attention.
Unusual persistent pain with a history of cancer, unexplained weight loss, or declining general health warrants medical advice. Progressive swallowing difficulty requires its own investigation. The frequency of osteophytes should not lead to dismissing every symptom in someone who has them.
When is imaging useful?
Radiographs show bony formations and the overall organization of a joint well. They can help when a diagnosis is uncertain, a fracture is suspected, or a specialist decision is being considered. However, they do not show every tissue or automatically determine the cause of pain.
MRI can examine nerve structures, the spinal cord, and certain soft tissues. CT describes bone in detail, particularly for targeted questions or planning. The choice depends on the clinical question rather than a wish to measure a growth regularly. [6] Repeating imaging without a clinical change or an expected effect on care often provides little useful information.
An incidental finding should be explained in simple terms. The aim is to avoid both excessive alarm and minimizing a result that truly matches the clinical picture. Clinical follow-up may be more relevant than repeated images for assessing recovery.
Conservative management: focusing on abilities
For knee or hip osteoarthritis, education and adapted exercise are among the recommended core interventions. [8] A program accounts for pain, strength, other health problems, and preferences. It does not aim to dissolve the osteophyte: functional improvement remains possible even if the bony image does not change.
Temporarily reducing an overly irritating load can support recovery. This may mean shortening a walk, breaking up a task, or alternating activities. Adjustment should not become permanent avoidance of all effort. Gradually developing the ability to tolerate more load is a more useful goal than seeking complete absence of sensation from the first day.
When weight management is relevant, it should be individualized, respectful, and compatible with preserving muscle. Assistive devices or workplace adjustments can also support independence. None of these options should be presented as an identical obligation for every joint or person.
Progressive rehabilitation and exercises
For a knee or hip, a program can begin with comfortable movements and accessible strengthening, such as an adapted sit-to-stand. Choose a difficulty consistent with current strength, then gradually increase one variable: repetitions, resistance, or duration. The following day’s response helps determine whether the dose was appropriate.
For the neck or back, exercises depend on the diagnosis and any neurological signs. Suspected spinal cord compression is not a situation in which movement should be forced. Without complications, mobility, endurance, and functional activities can be developed according to needs. The aim is not to “break” or reduce the growth through movement.
Simple monitoring can compare walking duration, ease of dressing, sleep, and recovery after activity. Moderate fluctuation does not necessarily indicate structural worsening. However, loss of strength, unusual swelling, or lasting deterioration requires reassessment.
Surgery is not decided on the osteophyte alone
An intervention may be discussed when concordant compression, substantial limitation, or severe joint disease persists despite appropriate management. The decision depends on the region, diagnosis, and balance of benefits and risks. Removing an incidentally discovered growth is not a goal in itself.
The CSAW trial of certain subacromial pain presentations found no clinically relevant additional benefit of decompression compared with placebo arthroscopy. [9] This result concerns a specific indication; it does not mean that every operation associated with a bony formation is useless. It nevertheless reminds us that a plausible mechanical explanation must be tested against trial results.
A realistic role for osteopathy and conclusion
Osteopathy does not make an osteophyte disappear or restore cartilage. Support may possibly help comfort and activity adjustment, with consent, but exercise recommendations do not demonstrate a specific osteopathic effect. Care should be reassessed if benefit is very brief or function does not improve.
A bony growth primarily calls for clinical interpretation. Understanding its location, looking for warning signs, examining other possible causes, and building progressive rehabilitation enables proportionate decisions. Success is measured through regained activities and quality of life, not necessarily the disappearance of a term from a radiology report.
Further reading: rotator cuff-related pain and the limits of the mechanical model.
References
- [1] Wong et al. Review Article: Osteophytes. Journal of orthopaedic surgery (Hong Kong). 2016.
- [2] Hunter et al. Osteoarthritis. Lancet (London, England). 2019.
- [3] Schaible et al. Osteoarthritis pain. Recent advances and controversies. Current opinion in supportive and palliative care. 2018.
- [4] Brinjikji et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. AJNR. American journal of neuroradiology. 2015.
- [5] Fang et al. The relationship between MRI-detected hip abnormalities and hip pain in hip osteoarthritis: a systematic review. Rheumatology international. 2024.
- [6] Sąsiadek et al. Degenerative disease of the spine: How to relate clinical symptoms to radiological findings. Advances in clinical and experimental medicine : official organ Wroclaw Medical University. 2024.
- [7] Fehlings et al. A Clinical Practice Guideline for the Management of Patients With Degenerative Cervical Myelopathy: Recommendations for Patients With Mild, Moderate, and Severe Disease and Nonmyelopathic Patients With Evidence of Cord Compression. Global spine journal. 2017.
- [8] Bannuru et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis and cartilage. 2019.
- [9] Beard et al. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet (London, England). 2018.
- [10] Zhang et al. EULAR evidence-based recommendations for the diagnosis of knee osteoarthritis. Annals of the rheumatic diseases. 2010.