Understanding tingling and supporting hand function
A hand that tingles at night, fingers that feel numb on waking or objects slipping from the grasp may suggest carpal tunnel syndrome. These symptoms deserve assessment, but do not identify the cause on their own. A medical diagnosis belongs to a qualified medical clinician. In the Quebec context, an osteopath can document functional difficulties, identify aggravating situations and offer appropriate support without replacing medical assessment. [1] [2]
The goals are practical: less disrupted sleep, more comfortable use of the hand and early recognition of worsening weakness. Activity adjustments, rehabilitation and sometimes surgery have different roles according to severity. Manual care may be considered as an adjunct with measurable goals and a clear explanation of its limits.
Anatomy: a narrow passage at the wrist
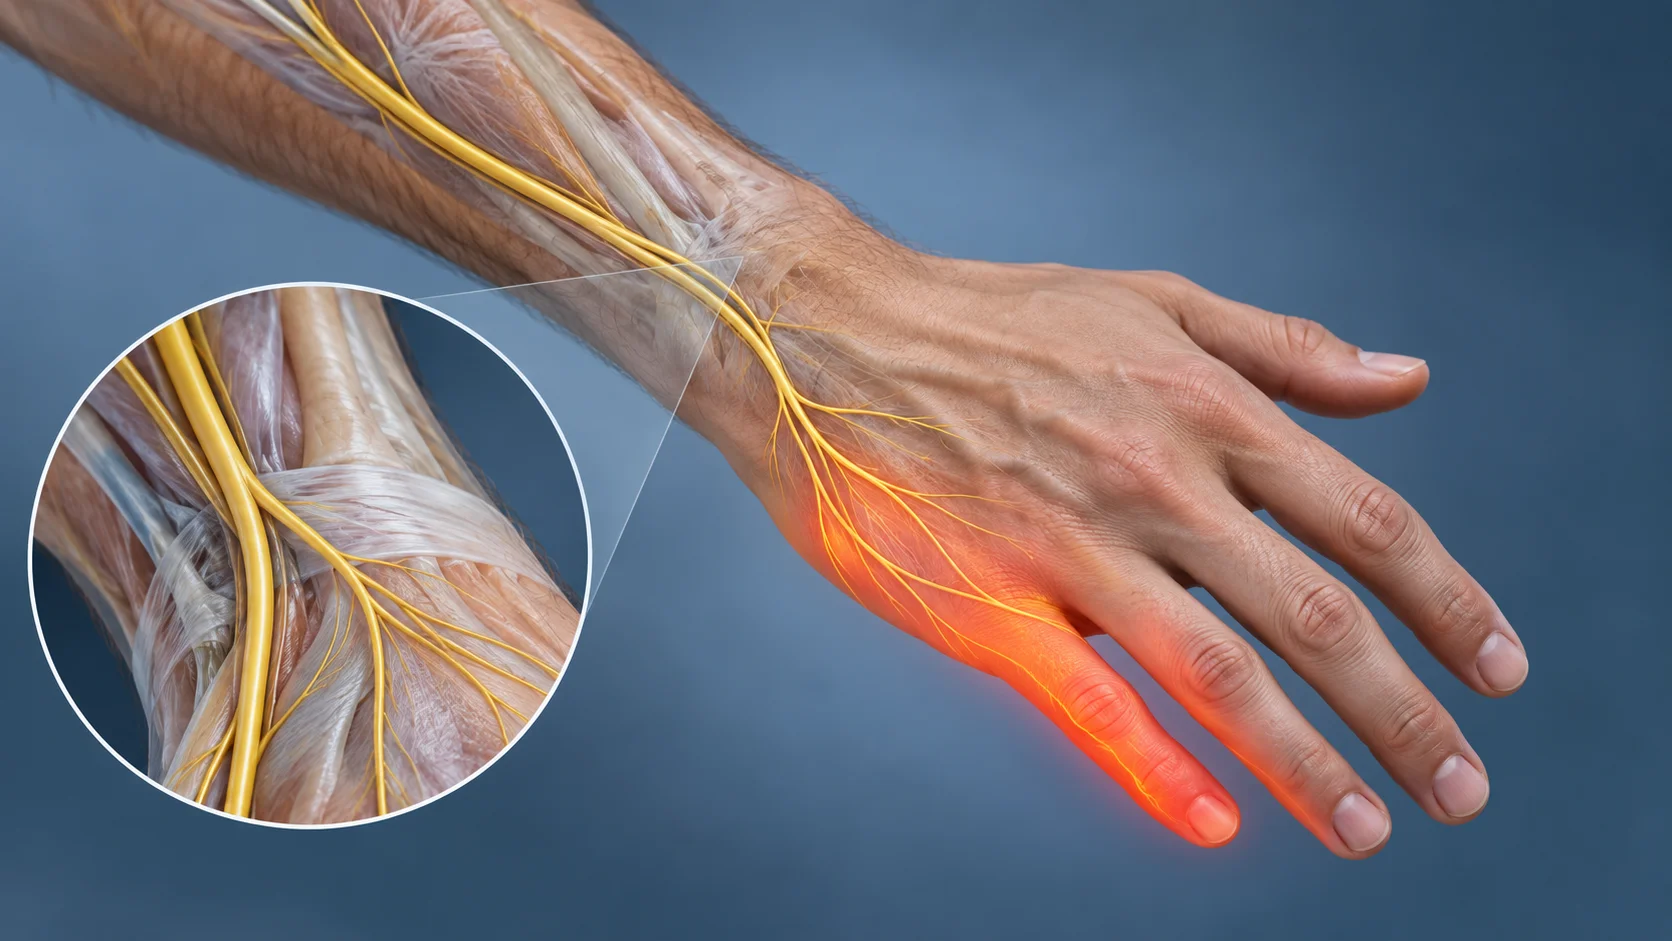
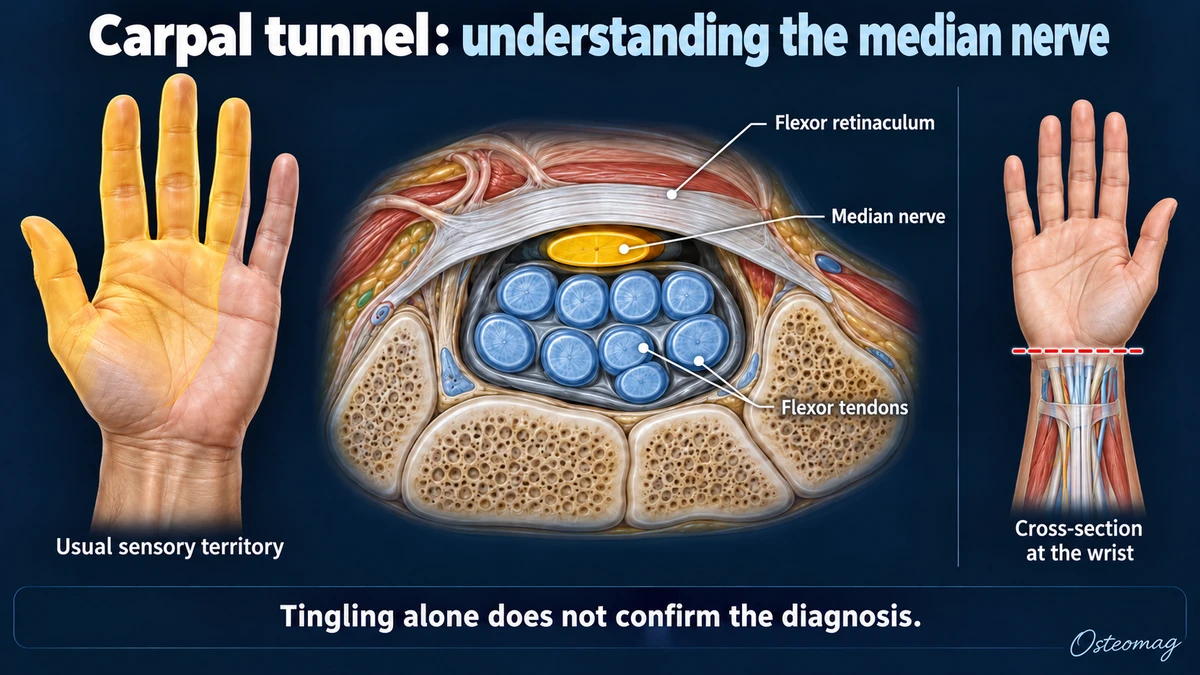
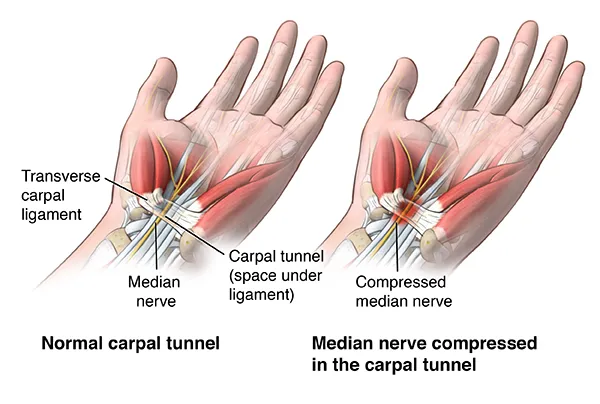
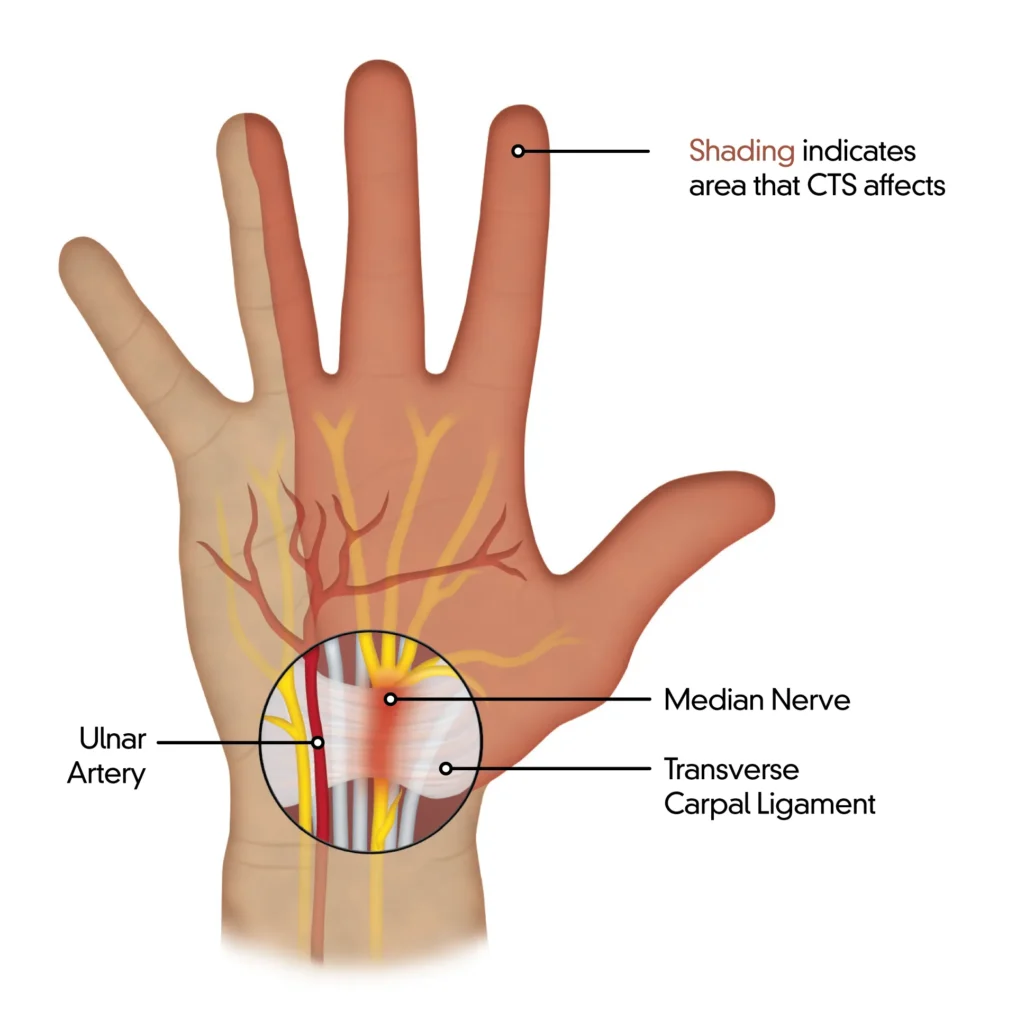
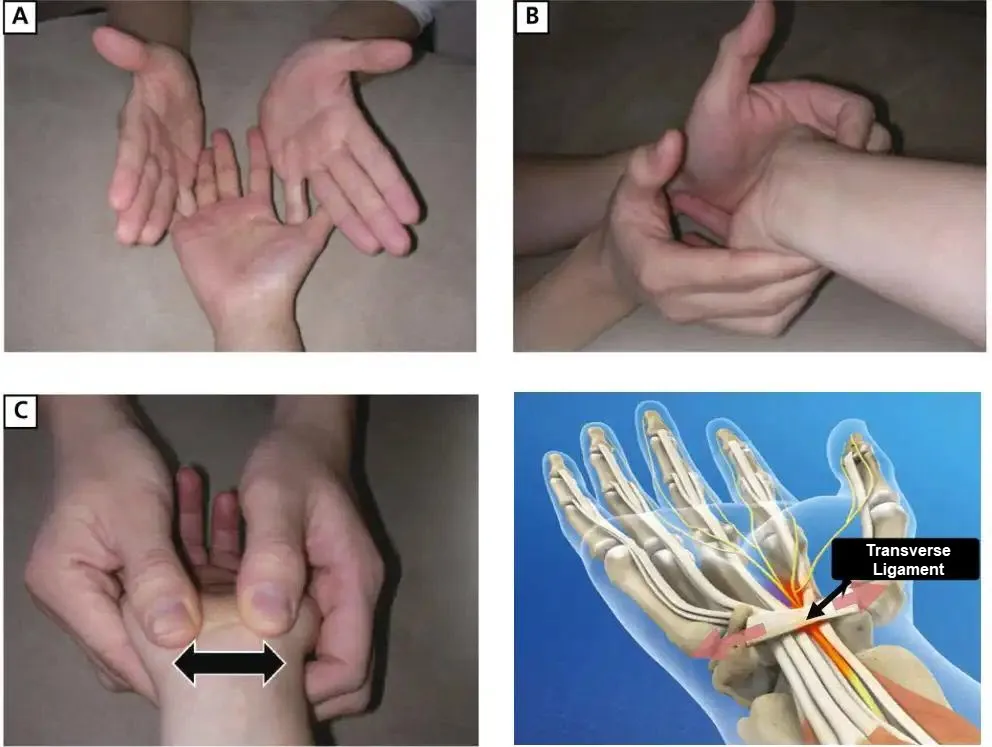
The carpal tunnel is formed by the carpal bones and covered on its palm side by the flexor retinaculum. The median nerve passes through it alongside nine flexor tendons. This nerve supplies sensation to the thumb, index and middle fingers and the thumb-side half of the ring finger, and contributes to some thumb muscle functions. The little finger mainly belongs to a different nerve territory. [2] [3]
Altered conditions within this passage can affect the median nerve. Pressure, tissue changes and individual vulnerability interact. A single explanation involving a displaced tendon or poor posture is too simplistic. Pain intensity does not always reflect the severity of nerve impairment. The sensory distribution is a useful clinical clue, rather than a home diagnostic test.
Symptoms: changes worth reporting
Tingling often occurs at night or during prolonged activities such as driving, holding a phone, reading or working with the hands. Some people shake their hand to seek relief. Discomfort can extend into the forearm. The distribution, duration and progression of sensations matter more than an isolated symptom. [2] [10]
With more significant involvement, numbness may become continuous, fine movements less precise or the thumb weaker. New difficulty fastening clothing, turning a key or holding a cup should be reported. These examples describe function and help a clinician assess change; they do not confirm the diagnosis.
Before a consultation, note which fingers are affected, when symptoms began, how often sleep is interrupted, which activities trigger discomfort and whether sensation returns fully between episodes. A few concrete examples make the discussion more useful and provide a baseline for follow-up.
Associated factors: avoid simplistic explanations
Carpal tunnel syndrome may be associated with anatomical characteristics, pregnancy, diabetes and certain inflammatory conditions. Tasks combining force, repetition and wrist loading can contribute to risk. Age and other individual factors also matter. An associated factor does not automatically explain one person’s symptoms. [2] [9]
Computer work is often blamed, but typing should not automatically be described as the cause. A useful analysis considers actual demands: gripping force, vibration, sustained positions, recovery and task organisation. It avoids blaming the person or prescribing a supposedly perfect posture.
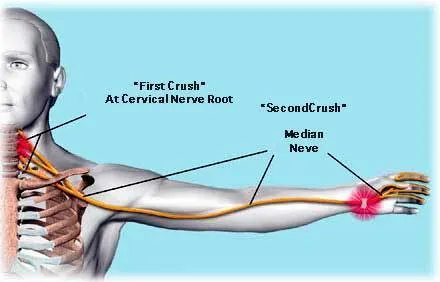
Neck pain and wrist symptoms can coexist. This does not prove that a problem in the neck causes compression at the wrist. A clinician may investigate more than one source when needed. A double-crush explanation should remain a hypothesis unless supported by the individual’s assessment.
Medical assessment and functional review
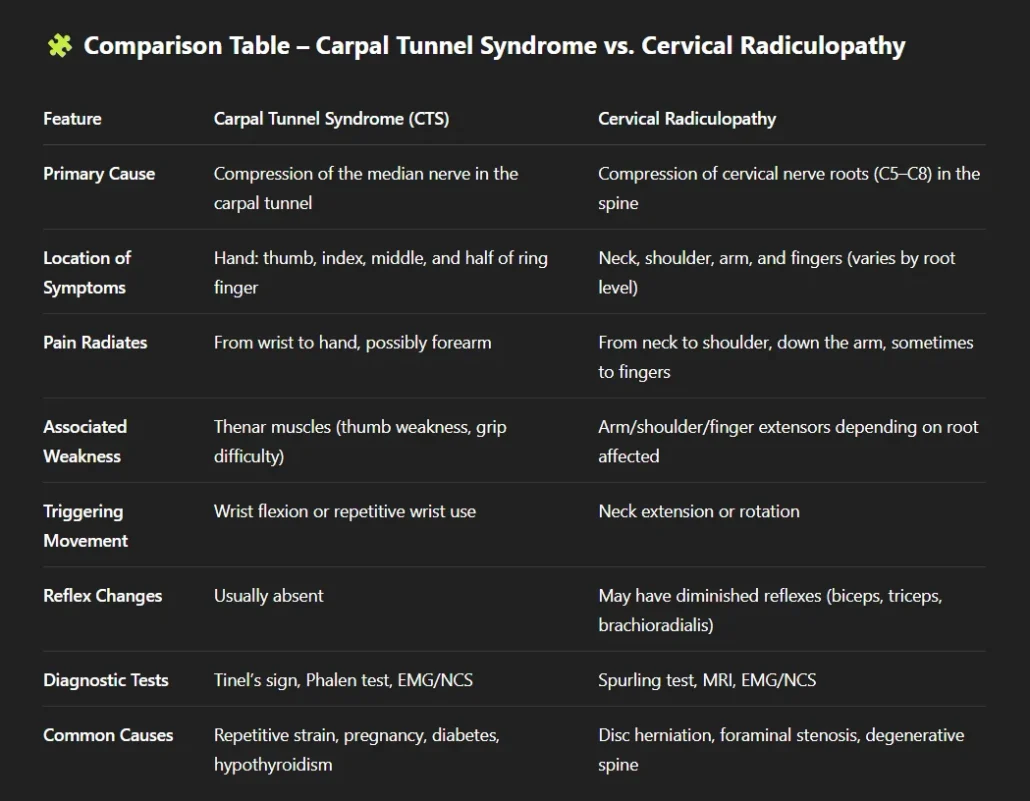
The clinician compares the history and examination with other possibilities, including a different nerve disorder, cervical involvement, joint disease or a more widespread neuropathy. Electrodiagnostic testing or ultrasound may help answer a specific question, but neither is automatically required for every presentation. [1] [2]
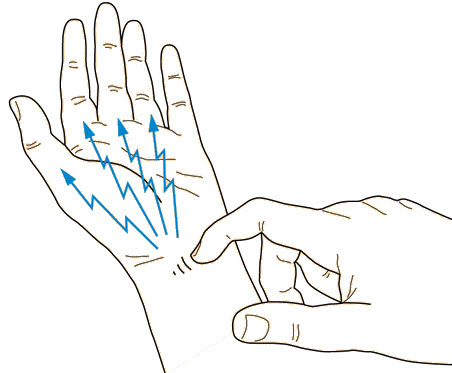
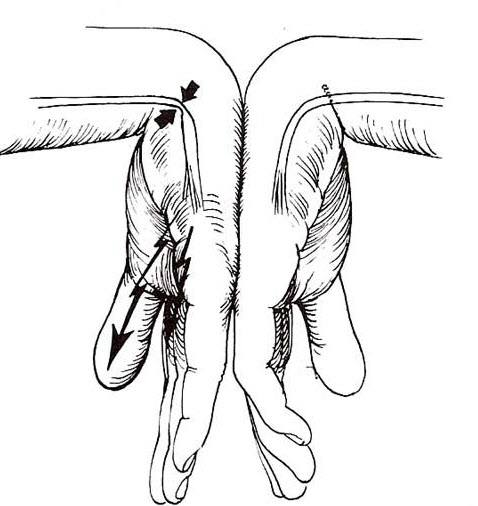
Tinel and Phalen manoeuvres can contribute to an examination, but cannot confirm or exclude the syndrome on their own. Repeatedly performing them at home can irritate a sensitive hand. Their interpretation depends on the full clinical picture, including sensation, strength and symptom history.
An osteopath’s functional review concerns difficult activities, comfortable mobility, movement tolerance and daily impact within the practitioner’s competence. The limits of these observations should be explained. Medical referral is needed when the diagnosis is uncertain, symptoms progress or the presentation does not suit adjunctive manual support.
Other causes and the choice of investigations
Symptoms mainly affecting the little finger suggest consideration of the ulnar nerve. Neck-to-arm pain with altered reflexes may suggest a cervical radiculopathy. A widespread neuropathy can affect multiple nerve territories. Local thumb pain may arise from a joint or tendon. These clues broaden assessment without providing a self-diagnosis. [2] [3]
The CTS-6 combines several history and examination findings. AAOS 2024 and JOSPT 2026 guidance supports its use by an appropriately trained clinician to assess the likelihood of carpal tunnel syndrome. Nerve conduction studies, electromyography and ultrasound address particular uncertainties, especially atypical symptoms. MRI is not a routine investigation for confirming a typical presentation. [1] [11]
When to seek care
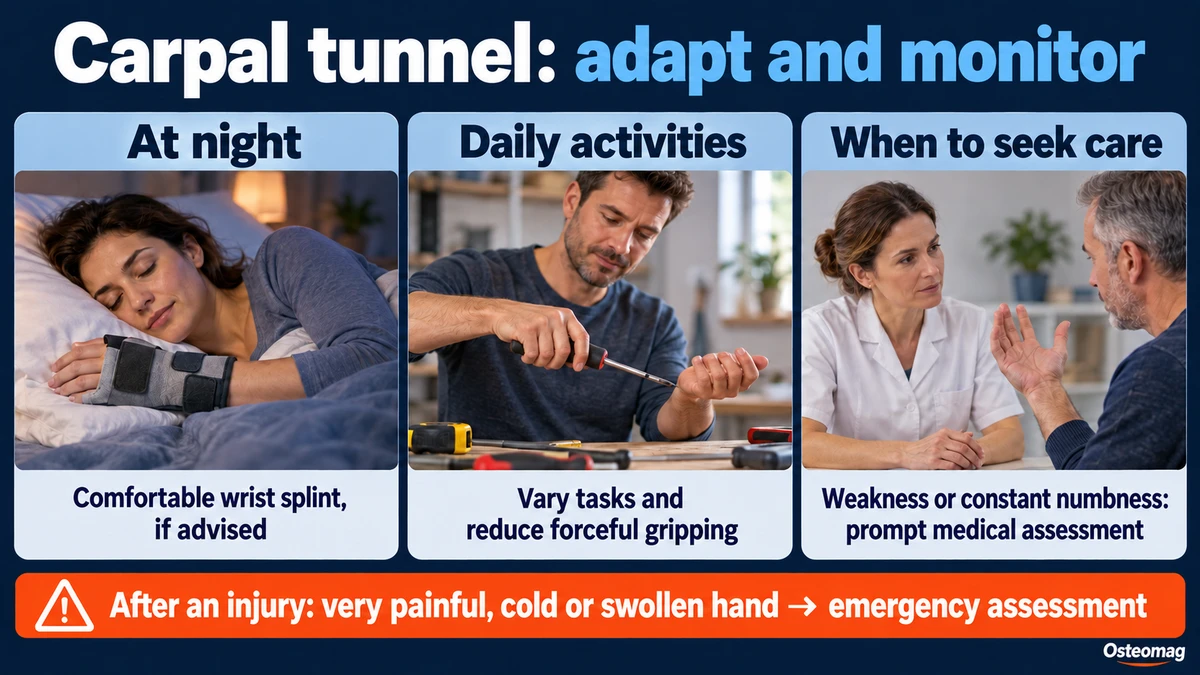
Repeated symptoms that disturb sleep or work also justify an appointment even without a severe warning sign. Pregnancy does not remove the need for monitoring. Temporary relief after a session should not overshadow persistent sensory loss: comfort and nerve function are different outcomes.
Adjust activities while maintaining everyday use
Identify positions and efforts that are poorly tolerated. Alternate tasks, temporarily reduce forceful gripping, use a more comfortable handle and interrupt sustained positions. Short, regular breaks are often more practical than abandoning every activity.
Try one adjustment at a time and observe its effect over several days. Holding a phone differently or dividing a task into shorter periods can reveal what actually helps. The goal is not to protect the wrist from all movement. Excessive restriction can complicate work, sleep and confidence in the hand.
Night splinting: an individual choice
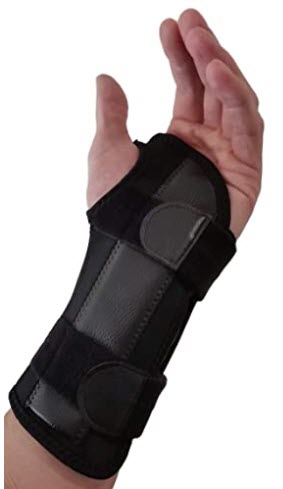
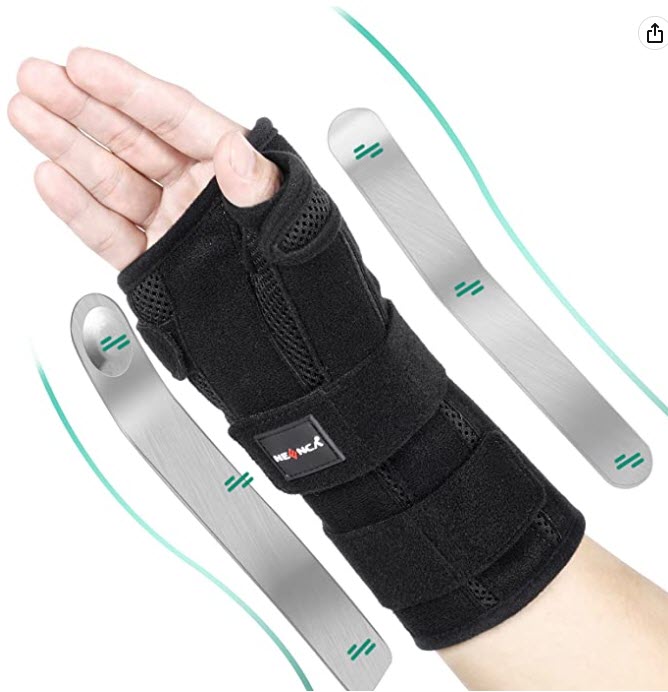
A wrist splint holding the wrist comfortably near neutral may be proposed. It should not feel tight or produce new symptoms. The Cochrane review describes uncertainty and modest or limited benefits depending on the outcome studied. A splint does not guarantee that surgery will be avoided. Selection and fit should be discussed with a competent professional. [4]
Rehabilitation: progress according to tolerance
Rehabilitation may combine education, activity adjustments and exercises chosen for the presentation. Comfortable hand and wrist movements can maintain everyday use. Nerve or tendon gliding requires individual instruction: provoking strong tension or sustained tingling is not a treatment goal. [5]
Exercise research has methodological limitations and does not support a promise of nerve recovery. Lasting aggravation, new weakness or increased numbness is a reason to stop the exercise and seek advice. Progression should follow the person’s response instead of a universal repetition count. The older Cochrane exercise review should also be read alongside the more recent 2026 clinical guideline. [5] [11]
| Situation | Goal | Useful action |
|---|---|---|
| Waking with tingling | Describe and reduce episodes | Track frequency; discuss wrist position and splinting. |
| Poorly tolerated manual task | Maintain adapted activity | Reduce gripping force and divide the task. |
| Exercise causes lasting discomfort | Avoid aggravation | Stop, adjust and seek advice. |
| Constant numbness or weakness | Protect nerve function | Obtain prompt medical assessment. |
| No measurable progress | Review the strategy | Coordinate care and reconsider referral. |
What osteopathic support can realistically offer
Osteopathic care may aim to improve movement comfort and support practical activity changes. It should not be presented as permanently freeing the nerve, mechanically changing tunnel dimensions or reversing nerve damage. Studies of manual physical therapy do not establish the effectiveness of every osteopathic practice.
Trials have investigated specific manual therapy programmes in selected groups and reported favourable findings on some outcomes. The four-year follow-up involved women and combined the interventions with home exercises. These results cannot be generalised to every patient, severe nerve impairment or any osteopathic session, and do not establish certain prevention of surgery. [7] [8]
Short-term symptom relief and a lasting effect must be distinguished. JOSPT 2026 allows certain manual approaches for short-term pain and functional improvement in mild to moderate cases. AAOS 2024 finds no demonstrated improvement in long-term patient-reported outcomes for several approaches, including manual therapy. Neither finding justifies a cure promise or delaying medical assessment. [1] [11]
What a consultation involves
The consultation reviews symptoms, work demands, leisure activities and previous care. The practitioner asks what the person wants to improve and explains each stage. Functional examination favours comfortable movements. Every intervention requires freely given consent; the person may decline a technique or stop the session.
If manual care is chosen, it should match tissue sensitivity. Strong pressure on a symptomatic nerve or repeated provocation is not automatically justified. One practical recommendation can complement the session. Follow-up compares night waking, difficult activities and new symptoms without multiplying appointments when benefit is absent.
Measure useful change
Choose a few indicators together: disturbed nights, tolerated activity duration and the ease of one specific task. Report reactions after care. Less pain accompanied by new weakness is not reassuring. If these measures stagnate, review advice and coordinate medical care rather than indefinitely repeating the same techniques. This keeps support proportionate to real needs.
When a different strategy is needed
Significant nerve impairment, worsening symptoms or an unsuccessful appropriate conservative plan may lead the clinician to discuss surgery. The decision considers function, severity, preferences and risks. Cochrane comparisons favour surgery over splinting for the rate of clinical improvement at six to twelve months, while other outcomes and comparisons are less clear. [1] [6]
After surgery, the surgical team’s advice guides return to activities. Adjunctive support focuses on comfort and function in coordination with that team. At every stage, the priorities are to recognise concerning changes, choose useful goals and provide honest information about what each approach can achieve.
References
- [1] American Academy of Orthopaedic Surgeons. Management of Carpal Tunnel Syndrome: Evidence-Based Clinical Practice Guideline. 2024.
- [2] Padua L, Coraci D, Erra C, et al. Carpal tunnel syndrome: clinical features, diagnosis, and management. Lancet Neurology. 2016;15(12):1273–1284. doi:10.1016/S1474-4422(16)30231-9.
- [3] Chammas M, Boretto J, Burmann LM, et al. Carpal tunnel syndrome – Part I: anatomy, physiology, etiology and diagnosis. Revista Brasileira de Ortopedia. 2014;49(5):429–436.
- [4] Karjalainen TV et al. Splinting for carpal tunnel syndrome. Cochrane Database of Systematic Reviews. 2023;2:CD010003.
- [5] Page MJ, O’Connor D, Pitt V, Massy-Westropp N. Exercise and mobilisation interventions for carpal tunnel syndrome. Cochrane Database of Systematic Reviews. Displayed version 2022;CD009899. doi:10.1002/14651858.CD009899. Literature search through January 2012.
- [6] Lusa V et al. Surgical versus non-surgical treatment for carpal tunnel syndrome. Cochrane Database of Systematic Reviews. 2024;1:CD001552. doi:10.1002/14651858.CD001552.pub3.
- [7] Fernández-de-las-Peñas C et al. Manual Physical Therapy Versus Surgery for Carpal Tunnel Syndrome: A Randomized Parallel-Group Trial. Journal of Pain. 2015;16(11):1087–1094. doi:10.1016/j.jpain.2015.07.012.
- [8] Fernández-de-las-Peñas C et al. Manual Therapy Versus Surgery for Carpal Tunnel Syndrome: 4-Year Follow-Up From a Randomized Controlled Trial. Physical Therapy. 2020;100(11):1987–1996. doi:10.1093/ptj/pzaa150.
- [9] Ghasemi-Rad M et al. A handy review of carpal tunnel syndrome: From anatomy to diagnosis and treatment. World Journal of Radiology. 2014;6(6):284–300. doi:10.4329/wjr.v6.i6.284.
- [10] National Health Service. Carpal tunnel syndrome. Patient information. Accessed 14 October 2026.
- [11] Erickson M et al. Hand Pain and Sensory Deficits: Carpal Tunnel Syndrome: Revision 2026. Journal of Orthopaedic & Sports Physical Therapy. 2026;56(4):CPG1–CPG79. doi:10.2519/jospt.2026.0301.