A difference felt under the fingers is an observation to interpret
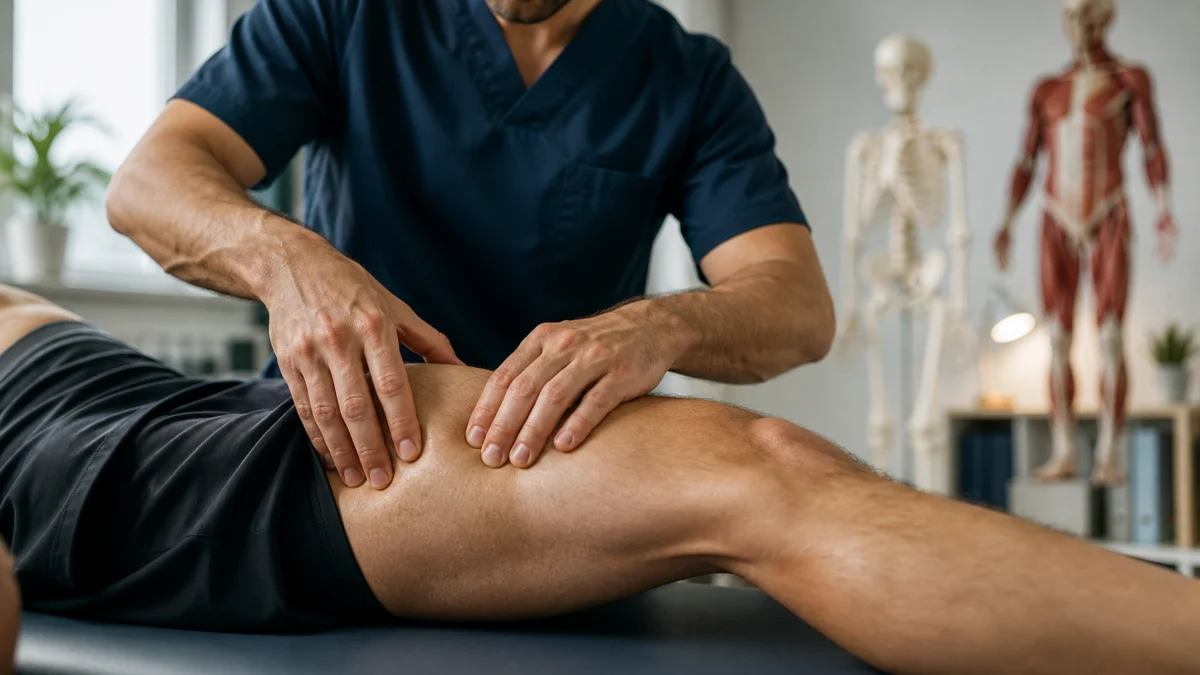
When an osteopath places their hands on a shoulder, one area may feel firmer than the other. The patient may also describe a sensation of tension, sometimes very clearly. These two experiences provide information, but they do not answer exactly the same question. The practitioner assesses resistance to touch; the person describes what they feel. The agreement between them is worth exploring, without immediately turning it into a diagnosis.
Yes, the hands can perceive certain differences. The difficulty begins when a specific cause is attributed to the sensation: shortened tissue, deep adhesion, or the definite source of the pain. Research on palpation shows different results depending on the task examined. A useful observation therefore requires a clear definition, a consistent method, and comparison with symptoms and movement.[1]
The key point
“This area feels more resistant today” describes an observation. To understand its importance, the next step is to check what changes for the person: their usual pain, movement, strength, and activities.
What does the word “tight” mean?
In conversation, this word may describe a muscle contraction, a feeling of stiffness, discomfort, or difficulty relaxing. In a mechanical measurement, stiffness refers to a system’s resistance to a given deformation. In a neurological examination, tone has yet another meaning. Using the same word for these phenomena encourages oversimplification.
A contracted muscle can change shape and become firmer. A different position also changes the tissues encountered under the fingers. Pressure passes through the skin and superficial tissues before reaching deeper structures. An overall sensation therefore does not make it possible to distinguish each layer automatically. Stating exactly what was observed is more informative than concluding that a “fascia is tight.”
The hand does not directly measure maximum force, structural length, or the electrical activity of a muscle. These properties require appropriate methods. Recognizing a visible and palpable contraction during a movement remains useful; attributing excessive or insufficient strength based on firmness alone raises another, much more difficult question.
Perceiving, reproducing, and explaining: three requirements
A sensation can be real without being reproducible between two examiners. Reliability refers to the agreement obtained when a test is repeated. Validity concerns its ability to measure what it claims to measure. Two people may classify an area in the same way without demonstrating that this classification identifies a lesion or the cause of the complaint.
In a review on low back pain, Nolet and colleagues report variable reliability for soft tissues and significant limitations for certain assessments of bony structures or mobility. These findings concern the tests studied and their protocols. They do not justify either declaring all palpation useless or guaranteeing every interpretation proposed during a consultation.[1]
A third requirement is clinical relevance: even if the observation is reproducible, does it change a useful decision? A difference that corresponds to no symptom, limitation, or goal may be of little importance. This question helps avoid multiplying corrections on a body that naturally has variations.
What stiffness studies teach us
Davidson and colleagues asked 125 physiotherapists to classify stiffness values produced by a device. The categories assigned through palpation overlapped considerably. This experimental model was not a complete examination of a patient: it tested a specific classification task. It calls for caution when a tactile impression is presented as a precise measurement.[2]
In a small study of 40 people with chronic neck or low back pain, Lederer and colleagues did not find a simple relationship between the more painful side and measured stiffness. This does not mean that mechanical properties never matter. It shows that a painful area cannot be assumed to be harder in every person.[3]
However, a meta-analysis of trunk muscles found, on average, certain differences in stiffness between groups with and without low back pain. The results vary according to the muscles and measurement conditions. An average difference between groups does not provide an individual diagnostic threshold. These findings can coexist with the previous study: they do not answer the same question.[9]
Observations to phrase clearly
| Observation | Possible interpretation | Useful check |
|---|---|---|
| The muscle hardens during a movement | Perceptible muscle involvement | Compare with relaxation and the requested task. |
| Pressure reproduces familiar pain | Sensitive area under the test conditions | Ask whether the sensation resembles the usual complaint. |
| One side feels firmer | Observed difference in resistance | Reproduce the position, point of contact, and pressure. |
| The skin glides less easily | Superficial resistance to movement | Describe the direction and examine the local context. |
| The area feels softer after treatment | Possible tactile change | Repeat the selected movement and listen to the patient’s response. |
| The person feels less stiff | Improvement in the person’s experience | Check its usefulness in activities and how long it lasts. |

This vocabulary leaves room for what is perceived while making the conclusion verifiable. For example, “this pressure reproduces your usual discomfort” indicates the person’s response. “This tissue is the cause of your pain” asserts an additional causal link. The second statement requires more evidence than the first.
Why the method changes the sensation
The point of contact, direction, duration, and intensity of pressure change what is being stressed. A supported shoulder does not present in the same way as a shoulder held actively. Even a right-left comparison becomes more difficult to interpret if the positions differ. Standardizing these parameters helps determine whether genuinely similar conditions are being compared.
Kothari and colleagues studied the standardization of the muscle-pressure stimulus. Under the conditions studied, a device provided more reproducible pressure than manual palpation. This finding highlights the value of defining the stimulus; it does not turn a pressure instrument into a universal lesion detector.[6]
Consent and comfort are also part of the method. The person can request lighter pressure, a different position, or an end to the contact. A protective reaction during an uncomfortable examination is not a fixed property of their tissue. The observation should specify what was happening when it was made.
Training can improve certain tasks
In a study by Degenhardt and colleagues, consensus training improved agreement between examiners for certain lumbar tests. The results were more favorable for tenderness to pressure and tissue texture than for certain asymmetries. The study demonstrates the potential to improve defined tasks, without validating every explanation that may be drawn from them.[4]
A subsequent four-month study examined whether this agreement was maintained with protocols and recalibration. Training, method control, and the question being asked therefore matter when interpreting the results. The practitioner’s personal experience remains different from external validation of their conclusions.[5]
This distinction can be explained simply to the patient: “We have reference points for describing this area, but we need to check how they relate to your difficulty.” It does not prevent the use of touch. It places the available precision in context and makes it possible to decide together which observations would be useful next.
Pain on pressure and tender points
A sensitive area can help locate the complaint or select tolerable contact. It does not automatically identify inflammation, an adhesion, or a lesion. The intensity of the stimulus and the person’s condition influence the response. Repeating strong pressure until a reaction is obtained does not increase the value of the observation.
The literature on palpatory identification of trigger points also has limitations in reliability. A name assigned to a sensitive area does not, on its own, provide a single mechanism of pain. It is preferable to specify the symptom reproduced and check whether it accompanies a relevant limitation.[8]
The person’s account remains essential. Pain created only by unusual pressure does not have the same meaning as a familiar sensation that occurs every time they lift a bag. In the first case, the examination may primarily have revealed a response to its own stimulus. In the second, an agreement worth exploring further is present.
The patient’s feeling of stiffness matters
Feeling stiff is a real experience, even when a mechanical measurement does not find an expected difference. An experimental study by Stanton and colleagues suggests that certain sensations of lumbar stiffness may reflect a protective interpretation by the perceptual system. This hypothesis is not a diagnosis applicable to everyone, nor a reason to ignore a complaint.[10]
The contemporary definition of pain recognizes a personal experience influenced by multiple dimensions. Listening to the patient helps in understanding the consequences of their sensations. It is therefore possible to look for changes in activity while avoiding reducing the experience to a single tissue property.[11]
Follow-up can focus on an everyday movement chosen together: looking behind oneself, carrying a child, or walking for longer. A concrete goal connects care to real life. The texture felt under the fingers becomes one piece of information among others, and the person can judge whether the improvement is useful to them.
What can instruments add?
Myotonometry and elastography quantify certain mechanical properties according to a protocol. Davidson and colleagues studied the reproducibility of myotonometric measurements on thenar and perineal muscles. This validation applies to the regions and conditions examined; it cannot be extended to all tissues without verification.[7]
A numerical value provides a measurement, not a complete explanation. Depth, position, or contraction may affect how it is interpreted. Instrumental tools are justified when required by the clinical or scientific question. They are not essential for every sensation of tension, and a more precise measurement does not automatically warrant treatment.
Checking the effect of treatment with the patient
After an intervention, the practitioner may perceive less resistance and the patient may feel more comfortable. Several mechanisms may contribute to the response, such as pain modulation or a change in muscle behavior. Scientific models of manual therapies do not allow a specific anatomical release to be inferred solely from the perceived outcome.[12]
A simple retest consists of repeating the same movement under comparable conditions, then asking what has changed. Immediate improvement is valuable when it facilitates an activity, but its duration and repeatability also matter. A temporary result can be useful without constituting proof of a permanent correction.
If the movement remains just as difficult even though the tissue seems more supple, the relevance of this target should be reconsidered. Continuing the same treatment solely to achieve a better tactile sensation risks losing sight of the objective. A lack of progress is information that can be used to adapt care, not a failing on the patient’s part.
Responsible palpation in osteopathy
Touch can guide an examination, adjust pressure, and support an attentive therapeutic relationship. Its use becomes clearer when the osteopath distinguishes between observations, hypotheses, and what remains unknown. Explaining the options and checking the person’s preferences contributes to shared decision-making.[13]
A new mass, unusual swelling, significant trauma, or neurological signs require appropriate referral. Palpation is not a substitute for necessary investigations and should not provide false reassurance about an evolving condition. When monitoring a common pain complaint, it is best combined with the patient’s history, abilities, and relevant signs.
Hands can therefore detect differences; understanding their significance requires broader reasoning. The aim is not to make every tissue identical or eliminate all variation. It is to support useful decisions, better-tolerated activity, and an understanding of the body proportionate to the available observations.
References
- [1] Nolet PS et al. Reliability and validity of manual palpation for the assessment of patients with low back pain. 2021.
- [2] Davidson MJ et al. Is it time to rethink using digital palpation for assessment of muscle stiffness? 2020.
- [3] Lederer AK et al. Tissue stiffness is not related to pain experience. 2019.
- [4] Degenhardt BF et al. Interobserver reliability of osteopathic palpatory diagnostic tests of the lumbar spine. 2005.
- [5] Degenhardt BF et al. Maintenance and improvement of interobserver reliability of osteopathic palpatory tests over a 4-month period. 2010.
- [6] Kothari SF et al. Standardization of muscle palpation: methodological considerations. 2014.
- [7] Davidson MJ et al. Myotonometry reliably measures muscle stiffness in the thenar and perineal muscles. 2017.
- [8] Lucas N et al. Reliability of physical examination for diagnosis of myofascial trigger points. 2009.
- [9] Vatovec R, Voglar M. Changes of trunk muscle stiffness in individuals with low back pain. 2024.
- [10] Stanton TR et al. Feeling stiffness in the back: a protective perceptual inference in chronic back pain. 2017.
- [11] Raja SN et al. The revised International Association for the Study of Pain definition of pain. 2020.
- [12] Bialosky JE et al. The mechanisms of manual therapy in the treatment of musculoskeletal pain. 2009.
- [13] NICE. Shared decision making. NG197.