

Lateral elbow tendinopathy: understanding elbow pain and rebuilding load tolerance
Lateral elbow tendinopathy, often called tennis elbow, is a painful condition mainly affecting the attachment of the wrist extensor tendons near the lateral epicondyle. Despite its name, it does not only affect tennis players. It frequently occurs in people whose work or leisure involves repeated gripping, wrist movements or sustained forearm effort. [1] [2] [3]
The term tendinopathy is often preferable to epicondylitis because changes in persistent cases involve more than a simple acute inflammatory process. The outlook is generally favourable, but recovery can be slow and fluctuate.
Anatomy and mechanisms
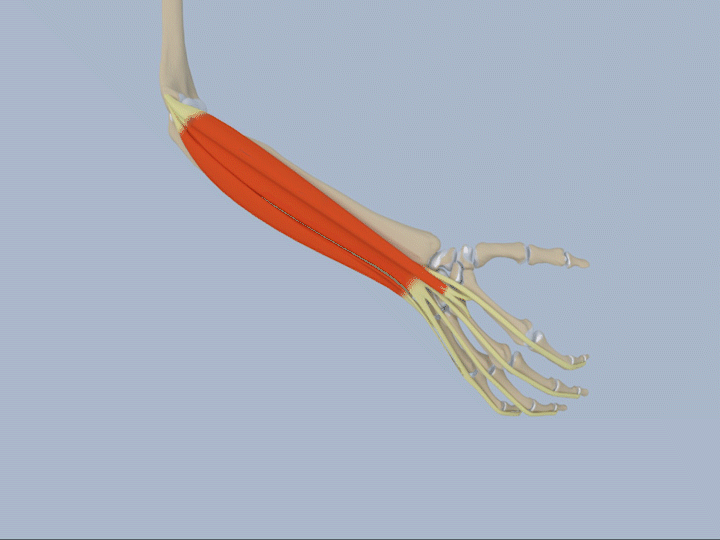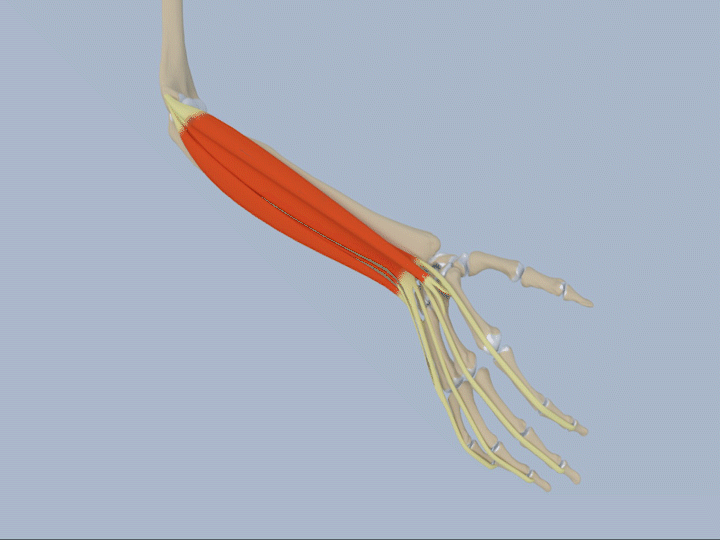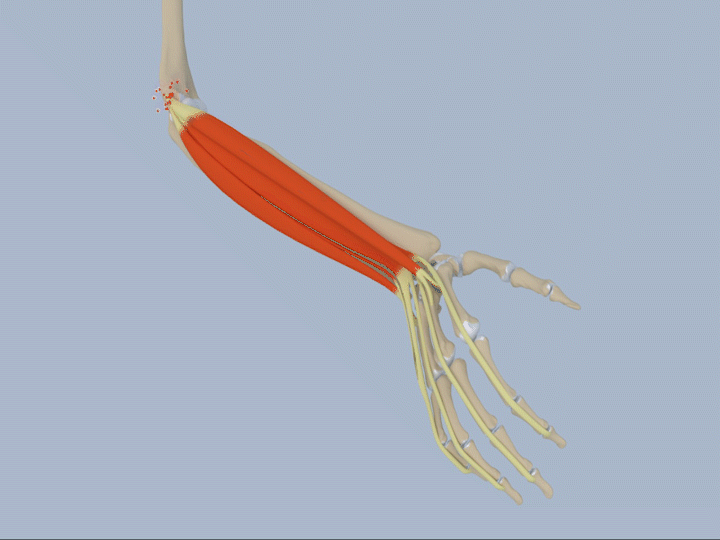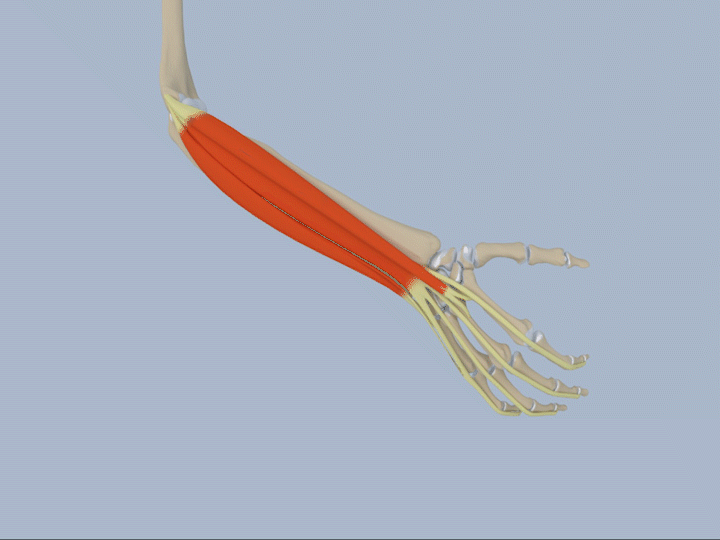
The extensor carpi radialis brevis tendon is frequently involved. This muscle helps stabilise the wrist during gripping. Pain can develop when load increases faster than the tendon can adapt. Contemporary models describe changes in tendon structure, sensitivity and mechanical capacity rather than inflammation alone. [4]
The nervous system, sleep, recovery, stress and expectations can also influence pain. An abnormal ultrasound finding does not necessarily explain symptom severity on its own.
Typical symptoms
- Pain on the outside of the elbow.
- Pain with gripping, carrying objects or shaking hands.
- Pain during resisted wrist extension.
- Tenderness near the lateral epicondyle.
- Reduced grip strength because of pain.
Pain may spread into the forearm. However, substantial numbness or tingling points more towards nerve involvement and calls for a different assessment.
Clinical examination
Diagnosis is usually clinical. The examiner tries to reproduce the familiar pain by palpating the tendon attachment, testing resisted wrist or middle-finger extension, or assessing a functional grip. No single test is perfect: interpretation depends on the overall history and examination.
It is also useful to examine the neck, shoulder, radial nerve, elbow movement and symptom-provoking tasks. This avoids reducing every case of lateral elbow pain to one structure.

Differential diagnosis
- Radial tunnel syndrome or radial nerve irritation.
- Cervical radiculopathy.
- Elbow osteoarthritis or another intra-articular disorder.
- Ligament injury after trauma.
- Fracture or another bone lesion.
- Pain referred from the shoulder or neck.
When to seek medical assessment
Pain after significant trauma, deformity, inability to use the arm, progressive loss of strength, fever, a hot swollen joint, increasing night pain or persistent neurological symptoms require medical assessment. Imaging is not usually needed in a typical case, but it may be indicated when the diagnosis is uncertain or the course is unusual.
Rehabilitation: progressive loading at the centre of care
Modern management aims to temporarily reduce loads that clearly exceed tendon tolerance without imposing prolonged complete rest. Activity is then rebuilt gradually. Wrist extensor strengthening is an important component, but the programme must reflect symptom irritability and functional needs. [5] [6] [7] [8]
An example of progression
- Sensitive phase: temporarily reduce highly provocative tasks and use comfortable isometric contractions.
- Strengthening phase: practise wrist extension against gradually increasing resistance while monitoring pain.
- Functional phase: gradually reintroduce gripping, lifting and work or sporting movements.
- Full return: increase volume, speed and repetitions according to tolerance.
Mild pain during exercise is not necessarily dangerous. A substantial, lasting increase in symptoms afterwards suggests that the load needs to be reduced.
Ergonomics and task modification
For someone doing repetitive work, temporarily adjusting volume, grip, tool weight or break frequency can reduce cumulative loading. In sport, technique, handle size, string tension and training volume can be reviewed. The aim is not a perfect posture, but a more manageable load.
The role of osteopathy
Osteopathic support may include movement advice and soft-tissue care for comfort, depending on the person’s preferences. Its specific benefit for tendon healing remains uncertain. Comfort care does not replace progressive activity and must not delay another assessment when indicated.
An osteopath can also help analyse tasks, monitor load progression and check whether the presentation remains compatible with lateral elbow tendinopathy. There is no need to put the elbow back in place or correct an assumed misalignment. Medical diagnosis and referral remain with appropriately qualified clinicians.
The existing historical diagrams below are retained from the previous English article. They do not establish that a visceral reflex causes tennis elbow or that treating such a reflex heals the tendon.
What calls for caution?
Comparisons between interventions are heterogeneous. Average exercise benefits are modest, and no programme guarantees rapid recovery. [6] Promises of a quick cure should be avoided. Recovery varies with symptom duration, occupational exposure, opportunities to adjust loading and individual factors.
Returning to sport or work
A full return is more appropriate when grip strength is improving, specific tasks are tolerated and the elbow’s response after effort remains acceptable. A gradual return is preferable to suddenly resuming full activity after complete rest.
Measuring what actually changes
Grip strength should be interpreted alongside pain: someone may grip less strongly because the task hurts, without having a neurological deficit. Progress can be tracked through a comfortable grip tested in the same position, ease of carrying a familiar object and discomfort at work. A specific questionnaire such as the PRTEE can also document pain and function. No isolated measurement decides readiness to return.
Research sometimes identifies strength differences beyond the wrist extensors alone. This supports a functional examination of the upper limb without assuming that shoulder weakness must be the cause. Strengthening should develop capacities relevant to the task rather than search for hidden chains of imbalance. [10]
Adjusting the exercise dose in daily life
One example involves supporting the forearm on a table, letting the hand extend beyond the edge and slowly raising the wrist against light resistance. Lowering is controlled. The elbow can remain in a comfortable position. Load and repetitions are chosen with the professional according to sensitivity, strength and experience. Someone with highly irritable symptoms may start with a shorter effort without movement.
Eccentric exercise describes work in which the muscle controls movement while lengthening, such as lowering the wrist. It is one studied option, not a unique solution. Strengthening trials and reviews report variable effects and do not support imposing the same recipe on everyone. [5] [7] [8]
The practical guide is the overall response: how does the session feel, and what happens later that day and the next day? If pain increases substantially, disrupts sleep or makes ordinary tasks harder, reduce one part of the programme. Once tolerance is stable, gradually increase one variable, such as weight or volume. Comfortable activities can continue to maintain general fitness.
Braces, splints and tools: a support to try thoughtfully
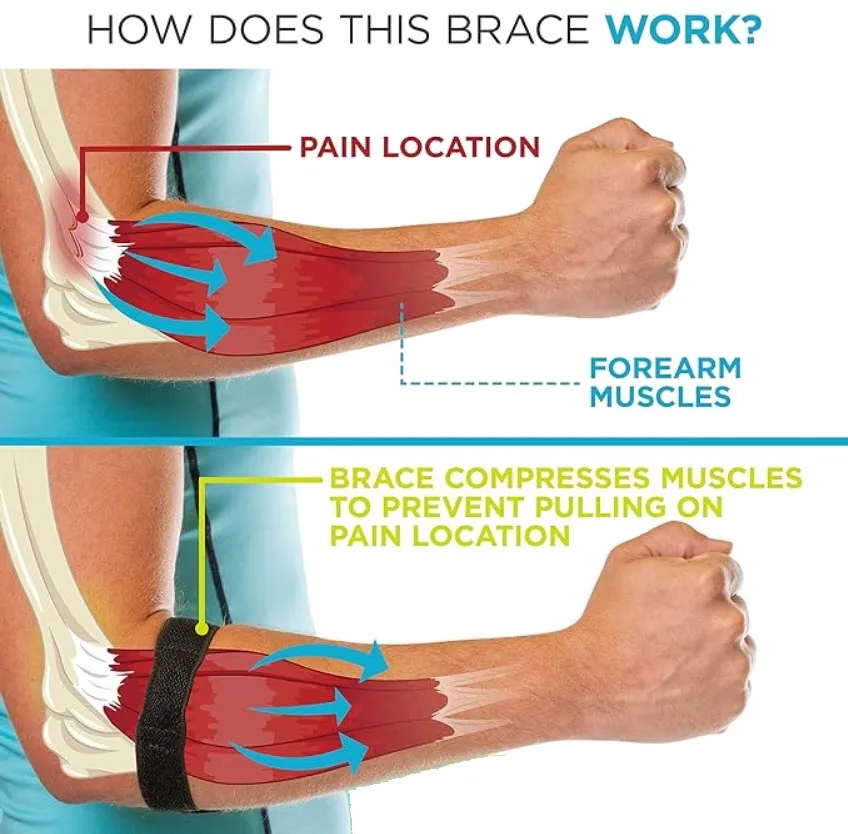
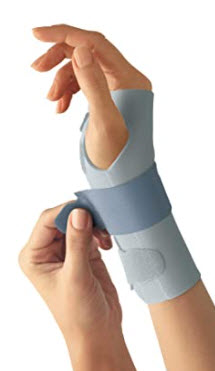
A wrist splint or forearm strap can temporarily change pain during a task for some people. Studies include immediate effects, which do not demonstrate tendon healing. Choice depends on comfort, intended use and individual response. A device that causes tingling, unpleasant compression or additional discomfort should be removed and reassessed. [9]
When carrying an object, using both hands, keeping the load close to the body or reducing its weight may make the task more comfortable. At work, spreading tasks out and varying grips avoids concentrating all difficult efforts into one period. These adjustments are temporary and negotiated around real needs. They do not mean the elbow is fragile or all movement must be avoided.

When should the diagnosis be reviewed?
Persistent typical pain warrants a review of loading, participation in the programme and the clinical explanation. Pain farther down the forearm, electrical sensations or weakness that does not appear pain-related may require a nerve assessment. Locking, a major loss of elbow extension or swelling suggests other structures may be involved.
Depending on the examination, an X-ray can investigate bone or joint disease, while ultrasound or MRI may answer a tendon-related question or clarify an atypical presentation. Imaging should not be used simply to check that the tendon looks perfect before every progression. Return decisions depend primarily on function, activity demands and the clinical trajectory. [2] [3]
Key points
- Lateral elbow tendinopathy is common and involves more than inflammation alone.
- Assessment is mainly clinical.
- Management centres on load adjustment and progressive strengthening.
- Manual comfort care can complement active rehabilitation, with uncertain specific benefits.
- Neurological symptoms, significant trauma or an unusual course call for further assessment.
| Situation | What it may mean | Practical response |
|---|---|---|
| Painful repeated gripping | Cumulative load exceeds current tolerance | Reduce volume, alternate tasks, then progress. |
| Exercise is tolerated and recovery remains stable | The dose is probably acceptable | Gradually increase one variable. |
| Numbness or progressive strength loss | The presentation may involve more than isolated tendinopathy | Seek medical reassessment. |
References
- Coombes et al. Management of Lateral Elbow Tendinopathy: One Size Does Not Fit All (2015).
- Lateral Elbow Pain and Muscle Function Impairments: clinical practice guideline (2022).
- BESS patient care pathway: Tennis elbow (2023).
- Millar et al. Tendinopathy (2021).
- The Beneficial Effects of Eccentric Exercise in the Management of Lateral Elbow Tendinopathy: A Systematic Review and Meta-Analysis (2021).
- Exercise interventions in lateral elbow tendinopathy have better outcomes than passive interventions, but the effects are small: a systematic review and meta-analysis of 2123 subjects in 30 trials (2021).
- Peterson et al. A randomized controlled trial of eccentric vs. concentric graded exercise in chronic tennis elbow (lateral elbow tendinopathy) (2014).
- Peterson et al. A randomized controlled trial of exercise versus wait-list in chronic tennis elbow (lateral epicondylosis) (2011).
- Evaluating the immediate effect of forearm and wrist orthoses on pain and function in individuals with lateral elbow tendinopathy: A systematic review (2020).
- An Investigation of Maximal Strength of the Upper Limb Bilaterally in Individuals With Lateral Elbow Tendinopathy: A Systematic Review With Meta-Analysis (2022).
Previously included video
This existing video is retained as supplementary material. It does not replace an individual assessment or the evidence and limitations explained above.


















