Respecting useful protection and gradually recovering movement options
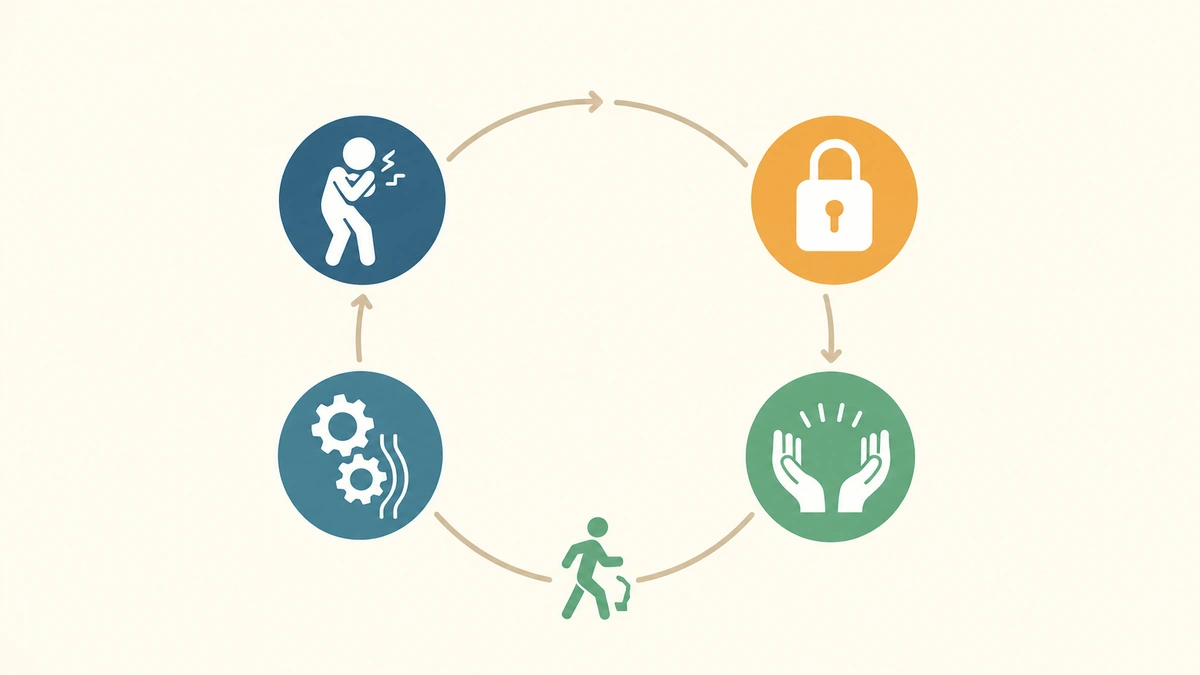
The human body continually adapts. After pain, injury or a period of overload, it may change how it moves, distribute effort differently between muscles, shorten a step, limit a range of motion or avoid a position. These changes are often helpful initially: they protect a sensitive area and allow continued function.
Problems arise when this temporary strategy becomes the only way to move. A person may then continue protecting an area long after the tissues have recovered enough to tolerate more load. What began as a solution can become a limitation.
In osteopathy, it is tempting to call this ‘compensation’ or ‘imbalance’. These words can be useful if they remain descriptive, but they should not suggest that a body has ‘malfunctioned’ or that every structure must be put back into place. Contemporary research on pain and motor control instead shows that adaptations are variable, individual and task-dependent.
Does pain really change how we move?
Yes. The work of Hodges and Tucker has profoundly influenced the modern understanding of movement in the presence of pain. Their model proposes that muscle activity is redistributed to protect the threatened area, rather than following a single pattern of contraction or inhibition [1].
Someone with back pain may therefore reduce lumbar flexion, shift more movement toward the hips or stiffen the trunk. Someone with knee pain may spend less time on the painful leg. Someone with shoulder pain may reduce speed or change the arm’s path.
These responses are not necessarily mistakes. They are often consistent with the immediate aim: avoiding an increase in pain.

Why can a useful adaptation become limiting?
A protective strategy becomes problematic mainly when it persists after the situation has changed. The motor system may retain a way of moving because it worked during the painful period, because the patient still anticipates pain, or simply because other options have not been explored again.
A 2023 systematic review of chronic nonspecific low back pain describes contradictory findings depending on the task: variability may increase, decrease or remain unchanged. The certainty of evidence is very low. The review therefore does not establish that persistent pain always reduces motor options or that every rehabilitation program should increase variability [2].
In other words, the problem is not necessarily that someone moves ‘badly’. It may be that they now have only a few available solutions.
Protection is not the same as fragility
When someone tenses before bending, they may interpret that response as proof that their back is fragile. The contraction may nevertheless simply be a protective strategy.
The practitioner’s language is therefore important. Saying ‘your back cannot support you’ or ‘your pelvis is unstable’ may increase fear. A more cautious formulation would be: ‘Your body seems to be using a lot of protection for this movement. Let us see whether it can gradually do it with less effort.’
This difference in wording changes the perspective: the aim is no longer to repair a defective structure, but to broaden a capacity.
When anticipation alone can change movement
These experiments involved, among other things, a small sample of healthy volunteers performing a particular task. They illuminate a possible mechanism, without determining the cause of a patient’s movement or confirming that a position is safe [3].
The motor system can change even before pain occurs. Experimental work has shown that anticipating pain can alter the recruitment of certain motor units [3].
This helps explain why a patient may stiffen when entering a position associated with previous pain, even if that position is no longer dangerous.
This anticipation is not imaginary. It is a real preparatory strategy. If it persists, however, it may unnecessarily restrict movement and reinforce a sense that the area is vulnerable.
Kinesiophobia: when fear of movement enters the picture
Kinesiophobia refers to excessive fear of movement associated with concern about pain or injury. It does not affect every person with pain, but it can contribute to avoidance and reduced activity.
A 2024 meta-analysis in adults with knee osteoarthritis found an association between kinesiophobia, pain, disability and functional limitation [4]. This relationship does not prove that fear is the sole cause of the problem, but it shows that it can become an important factor in some circumstances.
The practitioner’s role is not to force someone to ‘overcome their fear’, but to create sufficiently safe experiences for the patient to gradually test what is possible.
Should every compensation be corrected?
No. Compensation is not necessarily harmful. Someone with knee pain may use the hip a little more for a few days. An athlete may temporarily change technique. An older person may widen their base of support to feel steadier.
The useful clinical question is: does this strategy allow function without creating a substantial limitation?
If the answer is yes, temporarily retaining it may be preferable. Correcting it too early may increase irritability.
When is a compensation worth addressing?
It becomes more relevant when it:
- repeatedly increases pain;
- prevents an important activity;
- substantially reduces the available range of motion;
- persists long after tissue recovery;
- transfers excessive load to another area;
- maintains fear or dependence;
- limits sporting or occupational performance.
It is still necessary to show that a change actually improves function. Visible asymmetry alone is not enough.

How can an osteopath assess adaptation?
Protection and capacity: practical guidance
| Observation or situation | Cautious interpretation and possible next step |
|---|---|
| A movement remains restricted after improvement | Compare alternatives and their tolerance, without presuming an ongoing injury. |
| Asymmetry is visible but function is good | Appearance alone does not justify correction. |
| Activity causes lasting aggravation | Reduce the dose and reassess the symptoms and situation. |
| New weakness, trauma or general symptoms | Seek medical advice before continuing bodywork. |
The pain history, injuries, neurological symptoms and general signs come before trying alternatives. New weakness, loss of bladder or bowel control, significant trauma or unexplained worsening require appropriate medical referral. For uncomplicated low back pain, imaging is not routine: its relevance depends on clinical suspicion and what it would change [10].
Start with a real task
The best starting point is often a movement that matters to the patient: bending, climbing stairs, turning the head, raising an arm or walking.
The practitioner observes speed, range, effort and pain behavior. The aim is not perfect symmetry, but a functional strategy.
Compare several options
Once the movement has been observed, a variation can be proposed. For example, bend while allowing more hip movement, then try greater trunk flexion. The patient compares which option is more comfortable.
This comparison helps distinguish a genuine limitation from a protective habit.
Use palpation as a hypothesis
The practitioner may notice tenderness or greater tone in an area during palpation. That sensation does not prove that the tissue is ‘blocked’ or causes the compensation.
Palpation becomes more useful when linked to function and reassessment.
Can manual treatment modify a protective strategy?
Sometimes. Mobilization, muscle-focused work or a gentle technique may temporarily reduce pain and make movement easier. This improvement creates a useful opportunity.
If the patient remains passive and leaves without using the newly available range, however, the change may remain temporary.
A 2021 systematic review did not find manual therapy superior to no treatment or other treatments for kinesiophobia, fear avoidance or catastrophizing in chronic musculoskeletal pain. Certainty was low to very low. Manual care therefore cannot be presented as a proven way to erase fear; any temporary comfort must be assessed individually [5].
Reassessment: the central element
After an intervention, the same movement should be repeated. If the patient bent with apprehension, they bend again. If neck rotation was limited, it is reassessed.
The observed change may include:
- less pain;
- greater range of motion;
- less tension;
- faster movement;
- greater confidence.
A change does not prove that a vertebra or pelvis has been repositioned. It only shows that another strategy is available.
Why variability matters
A healthy motor system can solve the same task in several ways. This variability allows movement to adapt to fatigue, terrain, speed or load.
Rehabilitation may therefore aim to broaden options. For someone with pain, exploring several ways of walking, squatting or carrying a load may be helpful rather than imposing a single ideal technique.
Recent rehabilitation literature also emphasizes restoring neuromuscular performance beyond simple sets and repetitions, considering pain, control and the quality of activation [6].
Must exercise reproduce the ‘right’ posture?
Motor control models help construct hypotheses, not impose an ideal strategy. Exercise has favorable evidence on average for chronic nonspecific low back pain, but no result guarantees an individual response. When fear or distress substantially limits activity, qualified psychological support may complement a graded return [7] [8] [9].
Not necessarily. A perfect posture does not exist for every situation. The aim is instead to develop the ability to tolerate several positions.
A patient who has always avoided lumbar flexion may begin with small ranges, then gradually increase load. Someone protecting their shoulder may reintroduce faster movements when pain and strength allow.
Progression must respect the dose. Too little load does not stimulate adaptation; too much may reactivate symptoms.
Can protection represent progress?
Yes. After a recent injury, temporarily retaining a precaution may be the right decision. Using a stair rail, reducing speed or limiting an exercise for a few days may allow continued activity without exceeding tissue capacity.
Progress therefore does not mean immediately removing all protection. It means adjusting protection to what is actually needed.
How do we know when to reduce protection?
Several features can guide the decision:
- improving symptoms;
- quick recovery after activity;
- increasing strength;
- no signs of a substantial ongoing injury;
- greater confidence;
- tolerance of slightly more demanding tasks.
Progression should be gradual and reversible. If increasing load produces substantial, lasting aggravation, the plan is adjusted.

The danger of overly mechanical explanations
Saying that someone compensates because their pelvis is ‘twisted’ or a vertebra is ‘displaced’ can reinforce dependence. The patient may believe they cannot move properly until a practitioner has corrected their structure.
Motor control research instead shows that movement is produced by an adaptable system. Even when pain changes the strategy, it can gradually be relearned.
What osteopathy can reasonably contribute
An osteopath can:
- observe protective strategies;
- identify movements that genuinely limit function;
- use touch to help reduce some symptoms;
- reassess immediately;
- suggest movement variations;
- encourage progressive loading;
- refer when medical assessment or specialist rehabilitation is needed.
This role is important enough without promising to ‘correct every compensation’.
Conclusion
When the abnormal becomes normal, it is not necessarily because the body has malfunctioned. It may simply have learned a protective strategy that was useful at a particular time.
Modern practice distinguishes protection that is still needed from protection that has become limiting. The aim is not to remove every compensation or impose perfect symmetry, but to help the patient recover more options, strength, confidence and freedom of movement.
In osteopathy, touch may open a window. Active movement, reassessment and gradual progression can then help turn that opportunity into lasting capacity.
Scientific references
- [1] Hodges et al. Moving differently in pain: a new theory to explain the adaptation to pain. Pain. 2011;152(3 Suppl):S90-S98. doi:10.1016/j.pain.2010.10.020.
- [2] Alsubaie et al. Is movement variability altered in people with chronic non-specific low back pain? A systematic review. PLoS One. 2023;18(6):e0287029. doi:10.1371/journal.pone.0287029.
- [3] Tucker et al. Similar alteration of motor unit recruitment strategies during the anticipation and experience of pain. Pain. 2012;153(3):636-643. doi:10.1016/j.pain.2011.11.024.
- [4] Lozano-Meca et al. Association of kinesiophobia with pain, disability and functional limitation in adults with knee osteoarthritis: A systematic review and meta-analysis. Geriatr Nurs. 2024;60:481-490. doi:10.1016/j.gerinurse.2024.10.013.
- [5] Kamonseki et al. Effects of manual therapy on fear avoidance, kinesiophobia and pain catastrophizing in individuals with chronic musculoskeletal pain: Systematic review and meta-analysis. Musculoskelet Sci Pract. 2021;51:102311. doi:10.1016/j.msksp.2020.102311.
- [6] Murphy et al. Maximising neuromuscular performance in people with pain and injury: moving beyond reps and sets to understand the challenges and embrace the complexity. BMJ Open Sport Exerc Med. 2024;10(2):e001935. doi:10.1136/bmjsem-2024-001935.
- [7] Kantak et al. Linking Pain and Motor Control: Conceptualization of Movement Deficits in Patients With Painful Conditions. Phys Ther. 2022;102(4):pzab289. doi:10.1093/ptj/pzab289.
- [8] Hayden et al. Exercise therapy for chronic low back pain. Cochrane Database Syst Rev. 2021;9(9):CD009790. doi:10.1002/14651858.CD009790.pub2.
- [9] Williams et al. Psychological therapies for the management of chronic pain (excluding headache) in adults. Cochrane Database Syst Rev. 2020;8(8):CD007407. doi:10.1002/14651858.CD007407.pub4.
- [10] NICE. Low back pain and sciatica in over 16s: assessment and management. NG59. Recommandations.